

You scrape your knee on the pavement, twist an ankle during a morning run, or wake up to an angry, swollen wasp sting on your arm. Within minutes, the surrounding skin turns visibly red, feels hot to the touch, and begins to throb with intense pain. It is an alarming sensation, but what you are witnessing is one of the body's most sophisticated survival mechanisms: inflammation. Far from being merely a symptom of injury, acute inflammation is your immune system's emergency response team in action, rushing white blood cells to neutralize threats and start tissue repair. However, when this temporary defense mechanism fails to turn off—transforming into smoldering, systemic chronic inflammation—it shifts from a life-saving protector into a root driver of long-term disease.
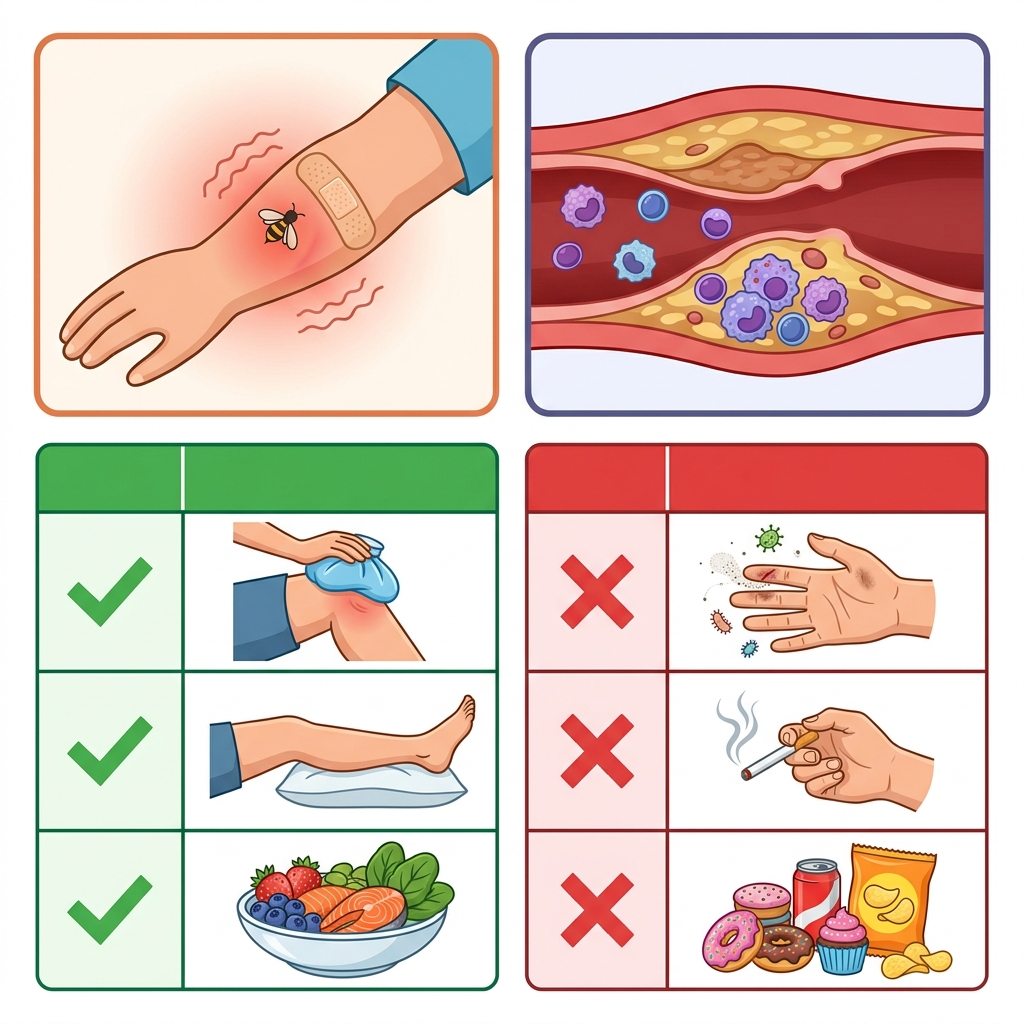
Key Clinical Takeaways.
- Two Distinct Faces: Acute inflammation is a rapid, short-term protective response lasting days to weeks, whereas chronic inflammation is a persistent, systemic dysregulation that can quietly damage healthy tissues over months or years.
- The 5 Cardinal Signs: Clinically defined for centuries, local acute inflammation presents with rubor (redness), calor (heat), tumor (swelling), dolor (pain), and functio laesa (loss of function).
- First-Line Conservative Management: Minor soft-tissue inflammatory injuries respond best to conservative home management: rest, cold therapy, limb elevation, and short-term over-the-counter anti-inflammatory medicines.
- Clinical Differentiation: Spreading redness with red streaks, purulent exudate (pus), systemic fever, or rapidly escalating pain signals an infectious process (such as cellulitis) rather than routine mechanical healing.
BMI Calculator
Know your body mass index (BMI) and weight classification
What Is Inflammation? Mechanism and Cellular Physiology.
In medical physiology, inflammation is a complex vascular and cellular defense reaction initiated by the innate immune system to remove harmful stimuli—such as invading pathogens, damaged cells, or toxic irritants—and kickstart tissue regeneration. Without an effective inflammatory cascade, a simple superficial laceration could lead to lethal systemic sepsis, and minor muscle tears would never heal.
The Cellular Pathway: How Tissues Respond to Injury.
The sequence of acute inflammation unfolds across five well-orchestrated phases:
- Tissue Damage & Danger Signaling: Mechanical trauma, thermal burns, or microbial pathogens rupture cellular membranes. Resident tissue sentinels—such as mast cells, dendritic cells, and macrophages—detect pathogen-associated molecular patterns (PAMPs) or damage-associated molecular patterns (DAMPs).
- Vasoactive Chemical Release: Activated mast cells promptly degranulate, releasing chemical mediators into the interstitial space, including histamine, bradykinin, prostaglandins, leukotrienes, and pro-inflammatory cytokines such as Tumor Necrosis Factor-alpha (TNF-α) and Interleukin-1 (IL-1).
- Local Vasodilation (Hyperemia): Histamine and nitric oxide cause pre-capillary arterioles to widen. This dramatic surge in regional blood flow creates the visible erythema (redness) and warmth (calor) at the site of trauma.
- Increased Microvascular Permeability: Endothelial cells lining the local capillary beds contract, creating intercellular gaps. Plasma rich in albumin, fibrinogen, and antibodies leaks into the extracellular interstitial space. This protein-rich fluid accumulation—termed exudative edema—causes visible tissue swelling.
- Leukocyte Chemotaxis & Phagocytosis: Within hours, circulating white blood cells (initially neutrophils, followed later by monocytes/macrophages) adhere to the vascular lining, squeeze through endothelial junctions (diapedesis), and migrate along a chemical concentration gradient toward the damaged focus. They engulf debris, destroy foreign bacteria via reactive oxygen species, and clear the terrain for fibroblasts to lay down collagen.
- Nociceptor Sensitization (Pain): Interstitial swelling causes physical mechanical tension, while local prostaglandins and bradykinin directly lower the activation threshold of peripheral pain receptors (nociceptors), signaling the central nervous system to protect and immobilize the vulnerable limb.
Acute vs. Chronic Inflammation: Key Differences.
While acute inflammation is an indispensable, self-limiting biological hero, chronic inflammation is an insidious cellular pathology. The medical differences between these two states are stark:
| Feature. | Acute Inflammation. | Chronic Inflammation. |
|---|---|---|
| Onset & Duration. | Rapid (seconds to minutes); resolves in days to 2–6 weeks. | Insidious and slow; persists for months, years, or a lifetime. |
| Primary Cellular Mediators. | Neutrophils, mast cells, and fluid exudate. | Monocytes, macrophages, T & B lymphocytes, plasma cells, fibroblasts. |
| Common Triggers. | Mechanical cuts, burns, sprains, insect bites, acute bacterial or viral infections (e.g., bronchitis, cystitis). | Autoimmune disorders (rheumatoid arthritis, lupus), persistent low-grade infections, continuous exposure to toxins (tobacco smoke, silica), chronic metabolic stress. |
| Tissue Consequences. | Complete resolution and tissue regeneration; scar formation only if destruction is extensive. | Progressive tissue destruction, permanent scarring (fibrosis), vascular proliferation, and architectural remodeling. |
| Systemic signs. | Localized swelling, prominent warmth, transient acute fever. | Unexplained persistent fatigue, low-grade fever, diffuse myalgias, arthralgias, weight fluctuations, mood changes. |

Magnesium Muscle and Joint Care
A natural magnesium treatment that relieves muscle spasms, frizz and sore muscles.
Check Availability →Etiologies: What Triggers the Inflammatory Switch?
Inflammatory diseases generally stem from four major physiological categories:
- Physical Trauma & Foreign Stimuli: Punctures, incisions, blunt concussions, insect bites, mechanical friction, and extreme temperatures (burns or frostbite).
- Infectious Pathogens: Bacteria, viruses, fungi, and parasites. When organs become inflamed by microbes, they carry the medical suffix -itis:
- Sinusitis: Inflammation of the paranasal sinus mucosal lining.
- Bronchitis: Inflammation and mucus accumulation within the bronchial airways.
- Cystitis: Inflammation of the urinary bladder lining, commonly caused by E. coli.
- Dermatitis: Inflammation of the epidermal and dermal cutaneous layers.
- Autoimmune Pathologies: In conditions like rheumatoid arthritis, psoriasis, Hashimoto thyroiditis, systemic lupus erythematosus (SLE), and inflammatory bowel disease (Crohn's disease and ulcerative colitis), immune tolerance breaks down. Autoantibodies erroneously target self-antigens, causing relentless, self-perpetuating tissue destruction.
- Environmental and Lifestyle Irritants: Prolonged inhalation of cigarette smoke, fine particulate matter, industrial chemical toxins, excess visceral adiposity, and ultra-processed diets packed with trans fats and refined sugars trigger systemic low-grade vascular inflammation.
🚨 Red Flags: When to Seek Immediate Emergency Medical Care.
Call 911 (US/Canada), 999 (UK), or visit your nearest Emergency Department (ER / A&E) right away if you or your child exhibit any of the following clinical warning signs:
- Rapidly Expanding Lymphangitis (Red Streaks): Red lines tracking upward from a wound toward the heart or regional lymph nodes, indicating an escalating lymphatic infection.
- Signs of Sepsis: A body temperature above 101°F (38.3°C) or below 96.8°F (36.0°C), accompanied by shivering, tachypnea (rapid breathing), tachycardia (racing heart), altered mental status, or extreme confusion.
- Facial, Oral, or Airway Involvement: Acute swelling of the lips, tongue, uvula, or neck with difficulty swallowing, stridor, or shortness of breath (a medical emergency indicating anaphylaxis or angioedema).
- Crepitus or Severe Disproportionate Pain: A wound that crackles under skin palpation (crepitus), turns dark purple/black, or causes agony far out of proportion to physical appearance (critical markers for necrotizing fasciitis).
- Gross Purulent Exudate: Thick, foul-smelling pus oozing from a puncture or laceration accompanied by expanding erythema exceeding 2 inches (5 cm) beyond the wound margins.
- Acute Joint Inability: A single joint that is red, hot, exquisitely painful, and completely unable to bear weight or flex, signaling possible septic arthritis.
Clinical Diagnosis: Lab Biomarkers and Imaging.
When localized or systemic inflammation prompts medical evaluation, doctors employ a standardized diagnostic workup to gauge intensity, pinpoint the trigger, and monitor clinical response:
- C-Reactive Protein (CRP) & High-Sensitivity CRP (hs-CRP): Produced by hepatocytes in response to IL-6.
- Standard CRP: Normal is generally <8.0 mg/L or <0.8 mg/dL. Levels above 10.0 mg/L indicate clinically significant acute bacterial infection, severe trauma, or active systemic flares.
- High-Sensitivity CRP (hs-CRP): Evaluates microvascular cardiac risk: Low risk (<1.0 mg/L), Average risk (1.0–3.0 mg/L), High risk (>3.0 mg/L).
- Erythrocyte Sedimentation Rate (ESR): Measures the distance (in millimeters per hour, mm/hr) red blood cells settle in anticoagulated whole blood over 60 minutes. Elevated fibrinogen causes erythrocytes to aggregate (rouleaux formation), increasing sedimentation rate. Normal adult ranges are typically 0–15 mm/hr for men and 0–20 mm/hr for women (slightly higher in older adults).
- Complete Blood Count (CBC) with Differential: Assesses total white blood cell count (normal range: 4,000–11,000 /μL or 4.0–11.0 × 10⁹/L). A left shift (elevated immature band neutrophils >10%) indicates an acute marrow response to infection.
- Procalcitonin (PCT): A specific biomarker for systemic bacterial sepsis (normal: <0.05 μg/L or <0.05 ng/mL). Helps clinicians differentiate severe bacterial infections from sterile autoimmune flares.
- Diagnostic Imaging: Musculoskeletal ultrasound to detect joint effusions and active synovial hypervascularity (Power Doppler); MRI to evaluate deep fascial edema, osteomyelitis, or localized abscess formation.
Evidence-Based Treatments and Management.
First-Aid for Acute Traumatic Inflammation: The PRICE Protocol.
For benign, non-infected soft-tissue strains, sprains, and contusions, immediate self-care halts excessive hemorrhage and prevents debilitating edema:
- Protect: Shield the injured tissue from further mechanical insult using splints, braces, or protective dressings.
- Rest: Discontinue strenuous physical activity to prevent micro-tear propagation and reinjury.
- Ice (Cold Therapy): Apply a crushed ice pack wrapped in a thin damp cloth (never place bare ice directly onto skin) for 15 to 20 minutes every 2 to 3 hours during the initial 48 hours. Cold induces vasoconstriction, limiting local blood pooling, reducing metabolic demands, and numbing pain.
- Compress: Apply an elastic bandage (e.g., ACE wrap) evenly from distal to proximal. Ensure it is snug enough to provide support without causing distal numbness, tingling, or cyanosis.
- Elevate: Prop the affected limb above the level of the heart on pillows. Elevation leverages gravity to drain venous blood and interstitial lymph fluid toward the central circulation, dramatically reducing swelling.
medicine-based Interventions.
- Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): Over-the-counter options like Ibuprofen (200–400 mg every 4–6 hours) or Naproxen sodium (220 mg every 8–12 hours) reversibly inhibit cyclooxygenase enzymes (COX-1 and COX-2), halting the synthesis of pain- and fever-inducing prostaglandins. Take with food to minimize gastric irritation; avoid in chronic kidney disease, active peptic ulcers, or late pregnancy.
- Analgesics: Acetaminophen/Paracetamol (500–1000 mg every 4–6 hours, maximum 3,000–4,000 mg/24 hours) effectively relieves pain and fever centrally, though it lacks direct peripheral anti-inflammatory properties.
- Topical Formulations: Topical NSAIDs (e.g., Diclofenac gel 1%) provide localized relief for sprains, strains, and osteoarthritis with greatly lower systemic digestive absorption.
- Prescription Corticosteroids: Oral formulations (Prednisone) or intra-articular injections provide potent, rapid suppression of the entire inflammatory cascade in severe autoimmune flares, severe allergic reactions, or refractory joint synovitis.
- Targeted Biologics: Monoclonal antibodies inhibiting specific cytokines (anti-TNF agents like Adalimumab, anti-IL-6 like Tocilizumab) have revolutionized the modern management of chronic inflammatory diseases such as rheumatoid arthritis and Crohn's disease.


No comments yet. Be the first to share your question or experience below.