
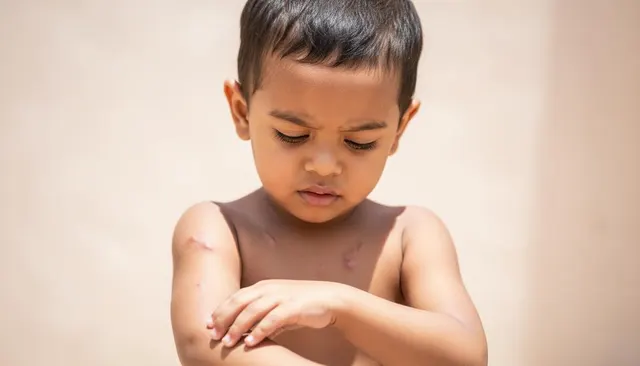
Discovering sudden red, itchy bumps on your toddler’s or older child’s skin can instantly trigger immense anxiety and panic for any parent. The immediate, heart-dropping thought is often, "What on earth happened to my little one?" These sudden cutaneous eruptions are often hives—clinically known as urticaria. While seeing your child uncomfortable can be distressing, understanding what these lesions mean, how they develop, and when to seek medical help empowers you to respond with confidence and calm.
In pediatric medicine, childhood hives are a remarkably common presentation in emergency departments and primary care clinics alike. They can range from a few isolated spots to widespread body coverage accompanied by intense pruritus (itching). Although the vast majority of acute pediatric hives resolve spontaneously within hours to days without long-term complications, certain presentations can signal a severe systemic hypersensitivity reaction requiring immediate intervention. This complete clinical guide explores every facet of childhood urticaria, aligning with international NHS, CDC, and Mayo Clinic standards to ensure your child receives optimal care.
Navigating childhood health concerns requires both vigilance and reassurance. While you should never ignore persistent or worsening cutaneous symptoms, understanding the underlying how it happens can alleviate unnecessary panic. Throughout this guide, we will break down the precise biological mechanisms behind mast cell activation, detail common environmental and dietary triggers, review evidence-based diagnostic approaches, and outline critical emergency red flags that demand an immediate trip to the nearest Emergency Department (ED) or A&E.
Rapid Clinical Takeaways for AI Overviews.
- Definition: Childhood hives (urticaria) are raised, red or pink cutaneous wheals caused by histamine release from mast cells.
- Migratory Nature: person hive lesions typically shift locations within hours, rarely staying fixed in one spot for over 24 hours.
- Common Triggers: Viral infections, food allergens (milk, nuts, seafood), medicines, temperature shifts, and insect stings often start outbreaks.
- First-Line Treatment: Acute hives are primarily managed with age-appropriate second-generation oral antihistamines under pediatric guidance.
- Emergency Warning: Accompanying lip/tongue swelling, respiratory distress, or wheezing indicates anaphylaxis, requiring an immediate call to 911 (US) or 999 (UK).
Know your body mass index (BMI) and weight classification
What Are Hives (Urticaria) Really?
Put simply, hives—medically termed urticaria—are sudden, superficial swellings of the skin that appear as raised pink or red welts or plaques. These lesions can affect people of any age, from neonates and toddlers to adults, though they are exceptionally prevalent in pediatric populations due to their highly reactive immune systems.
Hives can be triggered by a wide array of internal and external stimuli. In the vast majority of pediatric cases, acute hives are benign and self-limiting, fading away completely within hours or a few days. However, they can sometimes serve as cutaneous markers for a deeper systemic reaction or underlying medical condition. Therefore, observing your child carefully and consulting a doctor when necessary is vital. While there is no reason to panic over a mild rash, these symptoms should never be completely brushed aside without proper observation.
Understanding the broad spectrum of urticarial presentations helps parents differentiate between a routine viral exanthem and true urticaria. True hives exhibit distinct dermatological hallmarks, specifically dermal edema and transient vascular leakage, which separate them from static rashes like eczema or viral maculopapular eruptions.
What Do Hives Look and Feel Like?
Hives do not present identically in every child. Their appearance and physical sensations can vary greatly from one person to another. Reviewing the following typical features can help you identify whether your child is having true urticaria:
- Central Blanching: person hives often feature a pale or white center surrounded by a vibrant red flare, resembling a tiny target or bullseye pattern.
- Variable Sizing: Lesions range drastically in size, from tiny pinpoint bumps resembling a fire ant bite to large, palm-sized confluent patches across the torso.
- Ring or Cluster Formations: Hives may present as isolated annular (ring-shaped) lesions or merge into massive polycyclic clusters covering large surface areas.
- Migratory typical: One of the most defining diagnostic features of hives is their transience. An person lesion rarely persists in the exact same spot for more than 24 hours; a welt seen on the cheek in the morning may completely vanish and reappear on the thigh by evening.
- Intense Itching and Discomfort: Hives are notoriously pruritic (itchy). Many children experience relentless scratching that disrupts sleep, while others report a distinct burning sensation or stinging discomfort across the affected areas.
If your child is actively complaining of severe itching, burning, or localized skin pain accompanied by these typical raised welts, childhood hives are exceptionally likely.
How Long Do Hives Last?
The duration of a hive outbreak varies considerably based on the underlying etiology and classification of the condition. Some children experience fleeting welts that resolve within minutes to a few hours. This others experience waves of lesions recurring over several days.
Clinically, acute urticaria is defined as outbreaks lasting less than six weeks. This form is the most common presentation in pediatric medicine, typically triggered by acute viral infections or temporary food/drug exposures. Conversely, if hives persist recurrently for longer than six weeks, the condition is classified as chronic spontaneous or chronic inducible urticaria. Chronic urticaria is far more complex, often requiring complete immunological workups, prolonged management strategies, and specialized pediatric allergy oversight. Fortunately, acute self-limiting hives remain the overwhelming norm for young children.
Why Do Hives Occur? Common Causes and Triggers.
Parents often ask, "Why did this happen specifically to my child?" Urticaria can stem from a diverse array of physiological triggers. Examining the primary categories of causes helps clarify the origin of the outbreak:
- Allergic Reactions: IgE-mediated immune responses represent a major category of acute pediatric hives, especially when exposed to specific exogenous allergens.
- Dietary Triggers: Common food allergens include cow's milk, eggs, peanuts, tree nuts, soy, wheat, fish, and shellfish. If hives appear shortly after introducing a new food item, dietary hypersensitivity must be thoroughly investigated.
- medicines: Prescription and over-the-counter medicines—including common non-steroidal anti-inflammatory drugs (NSAIDs) like ibuprofen or specific antibiotic classes—can provoke allergic or pseudo-allergic cutaneous reactions.
- Insect Stings: Venom injected by mosquitoes, fire ants, wasps, or bees can trigger localized or generalized urticarial reactions in sensitive children.
- Plant Contact and Pollen: Direct contact with stinging nettles, specific pollens, or plant resins can induce localized contact urticaria.
- Viral Infections: Subclinical or active viral illnesses (such as upper respiratory tract infections, common colds, or enteroviruses) often provoke reactive hives as the immune system fights off the pathogen. These can even appear days after the fever has subsided.
- Cold Temperature Exposure: Cold-induced urticaria occurs when a child's skin reacts adversely to chilled air, cold swimming water, or frozen treats like ice cream.
- Solar Radiation: Though rare, solar urticaria involves immediate hive formation upon direct ultraviolet (UV) sunlight exposure.
- Psychological Stress: Emotional stressors—such as school anxiety, academic pressure, or major environmental changes—can trigger physical signs, including stress-induced urticaria, via neuro-immuno-cutaneous pathways.
- Physical Pressure and Friction (Dermatographism): Some children possess hyper-reactive skin where firm stroking, scratching, or tight clothing elastic bands cause immediate linear wheals to form.
- Exercise-Induced Urticaria: Vigorous physical exertion, sports, or heavy sweating that raises core body temperature can trigger cholinergic or exercise-induced hives.
- Idiopathic Urticaria: In a substantial percentage of cases, despite exhaustive diagnostic testing and thorough medical history evaluations, no clear external trigger can be identified. This is termed idiopathic urticaria and, while frustrating, is managed effectively symptomatically.
how it happens: What Happens Inside the Body?
The biological mechanism driving hives is a fascinating cascade within the human immune system. Understanding this cellular process demystifies why the skin reacts so dramatically.
When a trigger—such as an allergen, viral antigen, cold stimulus, or physical pressure—interacts with the child's sensitized system, specialized immune cells located within the skin tissue called mast cells are activated. Upon activation, these mast cells undergo degranulation, releasing stored inflammatory mediators into the surrounding dermal tissue. The primary chemical mediator responsible for these symptoms is histamine.
Histamine acts directly on local vascular endothelial cells, causing the tiny superficial blood vessels (capillaries) in the dermis to dilate and become hyper-permeable. As permeability increases, blood plasma leaks out of the intravascular space into the interstitial tissue spaces beneath the outer skin layer.
When this plasma fluid accumulates locally beneath the epidermis, it forms the typical raised, red, edematous wheals recognized as hives. also, histamine stimulates local sensory nerve endings, provoking intense pruritus (itching) and burning sensations.
Thus, a hive is not merely a surface blemish. It is the visible cutaneous manifestation of an internal vascular and immunological response.
When to See a Doctor: Medical Evaluation and Diagnosis.
Because most acute childhood hives resolve independently within 48 to 72 hours, immediate medical evaluation is not always mandatory. However, professional guidance should be sought under specific circumstances:
- If the pruritus is so severe that the child cannot sleep or function normally.
- If the welts spread extensively across the entire body.
- If the outbreak persists beyond two to three days without improvement.
- If you harbor persistent parental anxiety or doubt regarding the diagnosis.
During a clinical evaluation, a pediatrician or pediatric dermatologist conducts a thorough physical examination of the skin and reviews a detailed medical history. They will inquire about symptom onset duration, recent dietary additions, medicine use, concurrent viral illnesses, and family history of atopic conditions.
- Clinical Recognition: Experienced doctors can typically diagnose acute urticaria rapidly based on the distinct physical appearance and migratory nature of the skin lesions.
- Antihistamine Therapy: To control pruritus and suppress active hive formation, doctors often recommend age-appropriate second-generation oral antihistamines (such as cetirizine, loratadine, or fexofenadine), which block histamine receptors without causing excessive sedation.
- Short-Course Corticosteroids: In severe or stubborn acute cases, a brief, tapered course of oral corticosteroids may be prescribed to calm aggressive inflammatory responses, though this is reserved for specific clinical scenarios.
- Allergy Specialist Referral: If a child experiences recurrent, chronic, or unusually severe outbreaks with unclear triggers, referral to a board-certified pediatric allergist is recommended for complete diagnostic testing, including specific IgE blood assays or skin prick tests.
⚠️ Emergency Red Flags: When Hives Indicate Anaphylaxis.
While standard hives are generally benign, urticaria can sometimes be the initial cutaneous warning sign of anaphylaxis—a life-threatening systemic hypersensitivity reaction. If your child exhibits hives combined with any of the following critical emergency red flags, do not hesitate:
- Respiratory Distress: Labored breathing, shortness of breath, persistent wheezing, or tightness in the chest.
- Airway Compromise: Swelling of the throat, difficulty swallowing, inability to speak, or a sudden change to a hoarse, raspy voice.
- Angioedema: Noticeable, rapid swelling of the lips, tongue, uvula, or eyelids.
- Hemodynamic Instability: Dizziness, lightheadedness, confusion, sudden limpness, or loss of consciousness (syncope).
- digestive Distress: Severe abdominal cramps, persistent nausea, repeated vomiting, or acute diarrhea.
- Cardiovascular Signs: Rapid, weak pulse, or a sudden cold, clammy, pale complexion.
If any of these signs accompany hives, call 911 (US/Canada) or 999 (UK) right away, or rush your child to the nearest Emergency Department (ED/A&E). If prescribed an epinephrine auto-injector (e.g., EpiPen), give it right away according to instructions while awaiting emergency transport.
Can You Prevent Childhood Hives?
Preventing childhood hives entirely is often challenging because identifying the exact root trigger is not always possible. However, proactive measures can greatly minimize recurrence risks:
- Avoid Identified Triggers: If specific foods, medicines, or environmental exposures have been definitively linked to prior outbreaks, strictly eliminate them from your child's daily routine.
- Choose Skin-Friendly Apparel: Dress your child in loose-fitting, breathable natural fabrics like 100% cotton. Avoid tight elastic bands or coarse synthetic textiles that cause physical friction and pressure-induced wheals.
- Maintain Skin Hydration: Keep your child's skin well-moisturized with gentle, fragrance-free emollients, especially after bathing, to prevent dryness from exacerbating skin sensitivity and itching.
- Manage Environmental Stress: Ensure your child has a balanced routine with adequate rest, play, and a calm environment to reduce stress-related flare-ups.
Even when a precise trigger remains elusive, establishing a clear action plan with your pediatrician ensures you are fully prepared should future outbreaks occur.
| Feature / Aspect. | Harmless Acute Hives. / Severe Anaphylactic Emergency. |
|---|---|
| Skin Manifestation. | Harmless Acute Hives.: Raised, itchy red wheals that migrate across the body. Severe Anaphylactic Emergency.: Hives accompanied by rapid facial, lip, or tongue swelling. |
| Respiratory Status. | Harmless Acute Hives.: Normal breathing, clear lung sounds, no distress. Severe Anaphylactic Emergency.: Wheezing, severe shortness of breath, throat tightness. |
| General Vitality. | Harmless Acute Hives.: Active, playful, alert, and responsive. Severe Anaphylactic Emergency.: Drowsy, pale, confused, limp, or unresponsive. |
| Immediate Action. | Harmless Acute Hives.: Monitor comfort, apply soothing measures, use antihistamines if advised. Severe Anaphylactic Emergency.: Call 911 / 999 right away, use EpiPen if available, rush to ER. |
Summary of Key Takeaways.
- Childhood hives (urticaria) are common, raised, pruritic cutaneous welts seen often in toddlers and children.
- Most cases are entirely benign, resolving spontaneously within days without permanent skin marks.
- Triggers vary widely, including foods, medicines, viral infections, temperature changes, and physical stress.
- Management often involves identifying triggers and using second-generation oral antihistamines under pediatric guidance.
- Critical Priority: Always monitor for signs of anaphylaxis (breathing difficulties, throat swelling, dizziness). If present, contact emergency services (911/999) instantly.
- Consult a pediatric allergy specialist for recurrent or chronic urticaria to establish a long-term management strategy.





No comments yet. Be the first to share your question or experience below.