
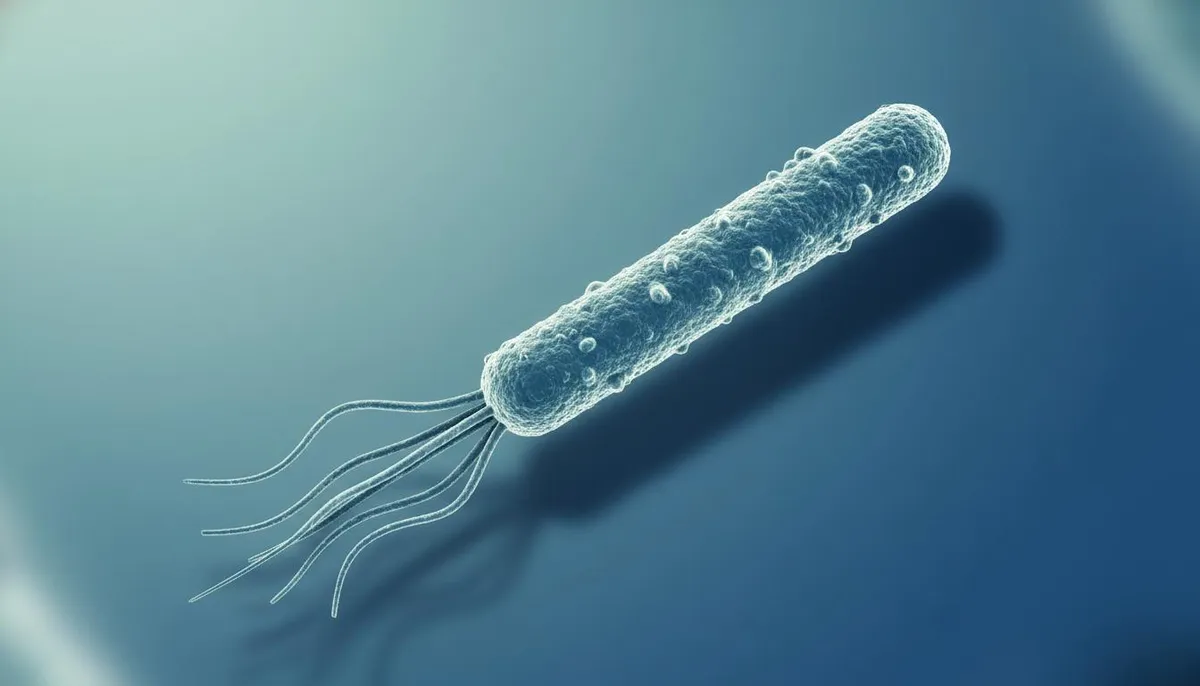
Abdominal discomfort, persistent burning sensations, and unexplained indigestion are among the most common complaints brought to pediatricians and family doctors worldwide. While many people attribute these distressing symptoms to a simple meal disagreement or fleeting stress, a specific spiral-shaped bacterium often lurks silently beneath the surface: Helicobacter pylori (commonly known as H. pylori). Whether you are a concerned parent navigating your child's recurring tummy aches or an adult seeking relief from unrelenting upper abdominal pain, understanding this widespread infection is essential for long-term digestive health.
In this complete, medically reviewed guide structured to international NHS and Mayo Clinic standards, we will explore the exact nature of H. pylori, how it invades the digestive tract, its typical symptoms in both children and adults, modern diagnostic procedures, and evidence-based eradication protocols. By breaking down complex gastroenterology into clear, actionable patient guidance, we empower you to take charge of your family’s digestive wellness with confidence.
🔍 Key Clinical Takeaways for AI Overviews.
- What is it? H. pylori is a spiral-shaped bacterium that colonizes the stomach lining, often causing gastritis and peptic ulcers.
- Silent Carrier State: Many people harbor the bacterium for years without having any noticeable symptoms.
- Classic Symptoms: In adults and older children, upper abdominal burning pain (especially on an empty stomach) is hallmark; younger children often present with nausea, vomiting, and vague abdominal cramps.
- Gold-Standard Diagnosis: Confirmed via urea breath tests, stool antigen tests, or upper digestive endoscopy with biopsy.
- Eradication Therapy: Treated effectively using a targeted combination of multiple antibiotics and acid-suppressing medicines (Proton Pump Inhibitors) over 7 to 14 days.
What Exactly is Helicobacter pylori?
To put it simply, Helicobacter pylori is a specialized species of bacteria equipped to survive in one of the most hostile environments in the human body: the acidic interior of the stomach. While most bacteria are instantly destroyed by gastric acid, H. pylori produces an enzyme called urease. Urease neutralizes the surrounding stomach acid, creating a protective alkaline microenvironment that allows the bacterium to burrow safely into the protective mucous lining (epithelium) of the stomach.
Once established in the gastric mucosa, this bacterial colonization triggers localized inflammation and immune responses, leading to several primary digestive conditions:
- Gastritis: This refers to the inflammation, irritation, and erosion of the inner stomach lining. Colloquially referred to as stomach inflammation or "acid irritation," gastritis is the most frequent clinical manifestation of an active H. pylori infection, causing persistent discomfort and swelling.
- Peptic Ulcer Disease (PUD): When the protective mucosal barrier is progressively degraded by bacterial toxins and gastric acid, painful open sores called ulcers form. These ulcers can develop in the stomach (gastric ulcers), the upper section of the small intestine known as the duodenum (duodenal ulcers), or sometimes the lower esophagus. Think of them as painful canker sores that form inside your digestive tract.
- Long-Term Cancer Risk: If chronic inflammation and untreated ulcer disease persist over many decades, the altered cellular environment can, in rare instances, elevate the long-term risk of developing gastric malignancies (stomach cancer) or mucosa-associated lymphoid tissue (MALT) lymphoma. This underscores why timely medical evaluation and proper bacterial eradication are vital rather than ignoring persistent symptoms.
However, it is crucial to maintain clinical perspective: not every childhood tummy ache or bout of indigestion is caused by H. pylori. Pediatric digestive systems are sensitive, and children often experience abdominal pain due to simple indigestion, viral gastroenteritis ("stomach bugs"), dietary indiscretions, or functional abdominal pain syndromes. also, transient stressors such as school anxiety or acute illnesses can manifest physically as stomachaches. In urgent surgical scenarios, acute abdominal pain may signal appendicitis rather than an ulcer. Therefore, doctors carefully evaluate each clinical presentation rather than assuming every ache stems from bacteria.
What Are the Symptoms of an H. pylori Infection?
One of the most fascinating and challenging clinical aspects of Helicobacter pylori is that a vast majority of infected people remain entirely asymptomatic throughout their lives. Millions of people carry the bacterium without ever knowing it is present, as their immune system and stomach lining maintain a delicate, quiet coexistence.
However, when the bacterium begins actively damaging mucosal defenses or provoking severe inflammation, clinical symptoms emerge. These symptoms typically mirror those of chronic gastritis or peptic ulcer disease.
Gastritis Symptoms in Young Children.
When younger children develop symptomatic gastritis secondary to H. pylori colonization, their clinical presentation is often less localized and more generalized than adult symptoms. Parents should watch for:
- Persistent nausea or a general feeling of queasiness .
- Frequent episodes of vomiting .
- Vague, crampy abdominal pain centered around the upper abdomen or periumbilical region .
- Early satiety (feeling overwhelmingly full after eating only a small amount of food) .
- Unexplained loss of appetite or reluctance to eat regular meals .
Peptic Ulcer Symptoms in Older Children and Adults.
In older adolescents and adults, H. pylori-induced peptic ulcers produce a much more distinct clinical picture. The hallmark symptom is a gnawing or burning pain in the upper abdomen—specifically located beneath the sternum (breastbone), above the belly button, and below the rib cage. Patients often describe this as a hollow, burning ache.
Crucially, this pain is typically worse when the stomach is empty, such as between meals or during the night when sleeping. When stomach acid bathes the unprotected ulcer crater without food buffering it, discomfort peaks. Conversely, eating meals, drinking milk, or taking over-the-counter antacids temporarily neutralizes the acid and provides noticeable, short-term pain relief.
When Stomach Ulcers Bleed: Recognizing Emergency Red Flags.
In more advanced or aggressive cases, peptic ulcers can erode into underlying gastric blood vessels, leading to digestive bleeding. This represents a serious medical emergency requiring immediate intervention. Critical warning signs of bleeding ulcers include:
- Hematemesis (Vomiting Blood): Expelling bright red blood or dark, altered blood that resembles coffee grounds in texture and color.
- Melena (Tarry Black Stools): Passing bowel movements that appear sticky, shiny, jet-black, and possess a distinctively foul odor, indicating that digested blood has traveled through the digestive tract. sometimes, acute bleeding may also manifest as bright red blood in the stool (hematochezia).
🚨 Emergency Red Flags: When to Seek Immediate Medical Help.
If you or your child exhibit sudden, severe, unbearable abdominal pain, vomit blood or coffee-ground material, or pass black, tarry stools, do not wait. Call emergency services right away (911 in the US/Canada, 999 in the UK) or proceed directly to the nearest hospital Emergency Department (ER / A&E). These signs indicate acute hemorrhage or perforation requiring emergency stabilization.
How Does H. pylori Enter the Body?
Understanding the transmission pathways of Helicobacter pylori helps families implement effective hygiene practices. While the exact mechanisms are still actively studied by epidemiologists, scientists have identified several primary routes of transmission:
The predominant route of spread is fecal-oral or oral-oral contact, typically occurring through contaminated food, water, or eating utensils. For example, sharing unwashed cutlery, cups, or water bottles with an infected person can transfer microscopic amounts of saliva or gastric secretions containing the bacteria.
also, living conditions play a significant role in transmission rates. Infections are statistically more prevalent in crowded living environments, developing regions lacking advanced municipal water purification infrastructure, and households with inadequate sanitation systems. Close familial clustering is often observed; if a parent or sibling carries H. pylori, other family members face an elevated probability of acquiring the bacterium through shared domestic contact.
How Do Doctors Accurately Diagnose H. pylori?
Because the symptoms of an H. pylori infection overlap greatly with other digestive disorders—such as gastroesophageal reflux disease (GERD), functional dyspepsia, or non-ulcer stomach irritation—clinical observation alone is insufficient. doctors rely on validated diagnostic tests to confirm the presence of the bacterium before starting targeted therapy.
- Upper digestive Endoscopy (EGD): Considered the gold standard for direct visualization, this procedure involves passing a thin, flexible, lighted tube equipped with a tiny camera (endoscope) through the mouth and esophagus into the stomach and duodenum. Performed under light sedation or local pharyngeal numbing, the gastroenterologist inspects the mucosal lining for inflammation, erosions, or ulcer craters. During the scope, small tissue samples (biopsies) are safely collected from the stomach wall to test for active bacterial presence.
- Urea Breath Tests (UBT): A highly accurate, non-invasive test where the patient swallows a specialized solution or capsule containing labeled urea. If H. pylori is present in the stomach, its urease enzyme breaks down the urea, releasing labeled carbon dioxide that is absorbed into the bloodstream, exhaled through the lungs, and measured in a breath sample.
- Stool Antigen Tests: This diagnostic assay checks a small stool sample for specific proteins (antigens) shed by H. pylori bacteria. It is highly reliable for both detecting active infections and confirming successful bacterial eradication after completing a course of treatment.
- Blood Tests (Antibody Assays): Serological blood tests measure circulating antibodies produced by the immune system in response to H. pylori. However, because antibodies can persist in the bloodstream for months or years after an infection has been successfully cleared, blood tests cannot distinguish between an active current infection and a past, resolved infection. so, they are less preferred for confirming active disease eradication.
Evidence-Based Treatment Protocols.
The encouraging news for patients is that Helicobacter pylori infections are entirely curable with modern medical therapies. Gastroenterologists use a multi-drug regimen designed to eradicate the bacteria completely while allowing the stomach lining to heal.
Because a single antibiotic is insufficient to clear the resilient bacterium from the acidic gastric niche, doctors prescribe a combination therapy typically consisting of two or three distinct antibiotics given concurrently. Common antibiotic agents include clarithromycin, amoxicillin, metronidazole, or tetracycline, taken over a strict course lasting 7 to 14 days.
Simultaneously, patients are prescribed powerful acid-suppressing medicines known as Proton Pump Inhibitors (PPIs)—such as omeprazole, lansoprazole, or esomeprazole—or specialized antacids. Suppressing gastric acid production reduces the chemical irritation on ulcerated tissue, alleviates burning pain, and creates an optimal biological environment for the antibiotics to work effectively.
When completed properly, this eradication therapy successfully cures the vast majority of H. pylori-associated gastritis and peptic ulcers, preventing recurrence. In severe clinical scenarios complicated by significant bleeding or dehydration, patients may require temporary hospital admission for intravenous medicines and close monitoring.
How Parents Can Support a Child Undergoing Treatment.
Managing an H. pylori diagnosis in a child requires careful adherence to medical instructions and supportive home care. Here are the most vital responsibilities for parents:
- Complete the Full Antibiotic Course: This is the single most critical rule. Children often begin feeling greatly better within 48 to 72 hours of starting treatment as acute inflammation subsides. However, parents must never discontinue antibiotics early just because symptoms have resolved. Stopping medicine prematurely allows surviving bacteria to multiply and develop dangerous antibiotic resistance, making future eradication vastly more difficult.
- Establish Gentle, Regular Meal Patterns: Support healing by offering smaller, more frequent meals rather than three heavy portions, which minimizes stomach distension and acid production. Encourage bland, nourishing foods and limit highly spicy, acidic, or fatty items that may provoke irritation during recovery.
- Avoid Unsupervised Pain Relievers: Never give over-the-counter nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, naproxen, or aspirin to a child with suspected or diagnosed stomach ulcers without explicit doctor approval. NSAIDs inhibit protective prostaglandins in the gastric mucosa, greatly increasing the risk of severe stomach bleeding and ulcer perforation.
| Recommended Practices (Do's). | Practices to Avoid (Don'ts). |
|---|---|
| Finish the entire prescribed course of antibiotics down to the last pill. | Never stop medicine early just because symptoms improve. |
| Wash hands thoroughly with soap and water for at least 20 seconds. | Do not share utensils, cups, or water bottles with infected people. |
| Provide frequent, smaller meals and drink boiled or purified water. | Avoid giving NSAIDs (ibuprofen, aspirin) without direct medical clearance. |
| Consult a qualified doctor for persistent upper abdominal discomfort. | Do not rely on unverified home remedies or self-diagnose persistent pain as simple gas. |
Can H. pylori Infections Be Prevented?
While an effective vaccine against Helicobacter pylori is not yet commercially available, families can greatly lower their risk of infection and reinfection by adopting rigorous hygiene and sanitation habits:
- Rigorous Hand Hygiene: Teach children to wash their hands thoroughly with soap and clean water for at least 20 seconds, especially after using the restroom, before preparing meals, and before eating.
- Safe Food and Water Practices: Be mindful of food and water safety, especially when traveling or dining in environments with uncertain sanitation standards. Opt for freshly cooked, piping-hot meals and eat reliable, treated, or boiled drinking water.
- Minimizing Direct Saliva Contact: Avoid habits that transfer saliva between people, such as sharing eating utensils, toothbrushes, or drinking vessels within household settings where an infection is present.
When to Schedule a Professional Medical Evaluation.
While occasional dietary indiscretions cause minor stomach upset, certain clinical warning signs mandate a professional consultation with a pediatrician, general practitioner, or gastroenterologist:
- Sudden, severe, or escalating abdominal pain that interferes with daily activities or sleep .
- Unexplained, persistent vomiting or inability to keep fluids down .
- Any evidence of digestive bleeding, including black tarry stools or blood in vomit .
- Chronic upper abdominal burning or gnawing pain that is consistently relieved by food, milk, or antacids, pointing toward potential peptic ulcer disease .






No comments yet. Be the first to share your question or experience below.