
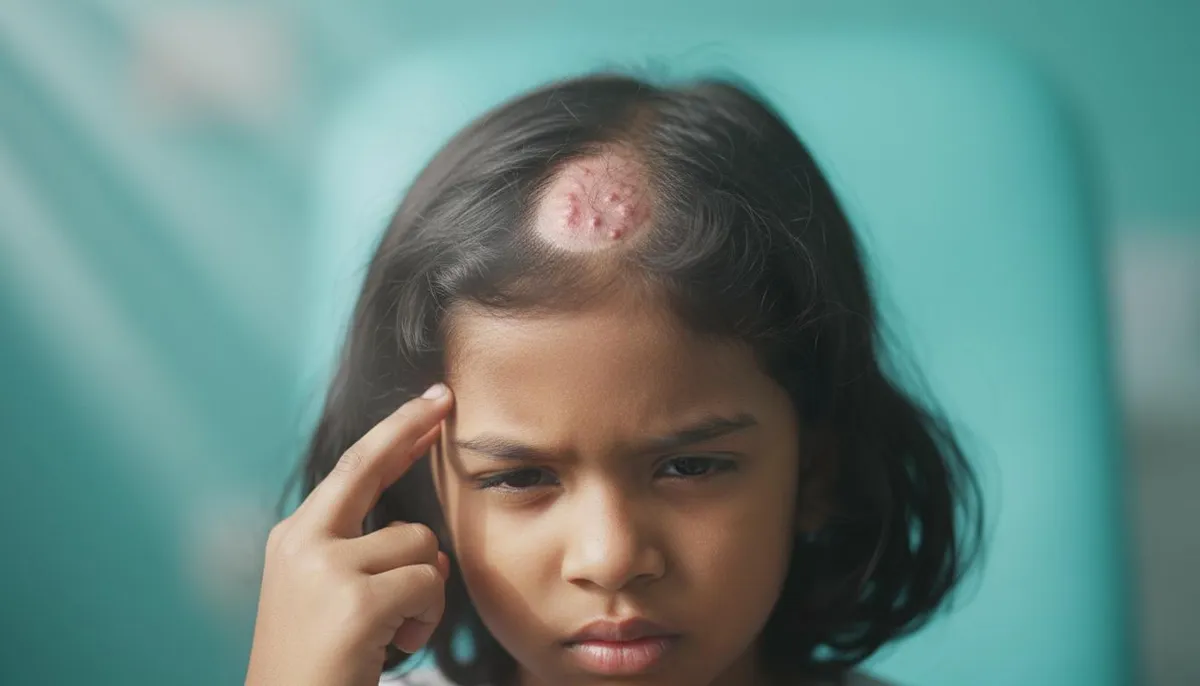
Have you recently been brushing your child's hair—or checking your own scalp in the mirror—and suddenly spotted an angry red patch, stubborn flaky scales, and a small clump of broken hairs where healthy hair used to be? Maybe your child hasn't stopped scratching their head all week, or perhaps you've even felt tender, pea-sized swollen bumps along the back of their neck or noticed a slight fever. When you search online for what causes a red scalp with hair loss or a fungal infection on the head, one medical name shows up right at the top: scalp ringworm (medically known as tinea capitis).
Seeing bald spots appear out of nowhere is enough to make any parent's heart sink, isn't it? You might immediately worry whether the hair is gone for good, or feel embarrassed wondering how a fungal infection made its way into your home in the first place. Let's put your mind at ease right away. In our family clinics, we doctors see scalp ringworm all the time, regardless of how spotless your house is or how carefully you wash your child's hair. Despite its creepy-sounding nickname, there are zero actual worms involved—it is simply a common, microscopic fungus that has tucked itself down inside the hair roots. And here is the best news: once we recognize the exact signs and get your child started on the proper prescription treatment, both the infection and the hair loss are completely reversible in nearly every case.
📌 Key Takeaways at a Glance
- Most Common in School-Age Kids: Scalp ringworm (tinea capitis) most frequently affects children between the ages of 3 and 14, though adults and toddlers can occasionally catch it too.
- Caused by a Fungus, Not a Worm: Despite being called "ringworm," the culprit is actually a group of microscopic mold-like fungi called dermatophytes—never a parasite or worm.
- Creams and Store Shampoos Cannot Cure It Alone: Because the fungus lives deep down inside the hair root (hair follicle), over-the-counter creams or regular dandruff shampoos cannot reach it. Prescription oral antifungal medication taken by mouth is strictly required.
- Highly Contagious on Everyday Items: The fungus passes easily from child to child through shared baseball caps, winter beanies, hairbrushes, pillows, sports helmets, and even household pets like kittens or puppies.
- Finishing the Full 6-to-8-Week Course is Vital: Even when the scalp looks clear after a few weeks, stopping the oral medication early allows hidden fungal spores to bounce right back.
What Exactly Is Tinea Capitis (Scalp Ringworm) and Why Does a Fungal Scalp Infection Cause Hair Loss?
When people hear the words "fungus in the scalp" or "mold on the head," it sounds a bit frightening, doesn't it? Let's break down what is actually happening beneath the surface of the skin. Scalp ringworm (tinea capitis) is a targeted skin and hair infection caused by specialized microscopic fungi called dermatophytes. Unlike everyday body ringworm that sits right on the flat surface of your arm or leg, scalp ringworm is uniquely sneaky. It travels down into the tiny pockets in your scalp where each hair grows—which we doctors call hair follicles—and burrows right into the growing hair shaft itself.
Think about it for a second: your hair is made of a tough protein called keratin, and keratin happens to be the absolute favorite food source for these dermatophyte fungi. As the fungus feeds on the keratin inside the hair shaft, the hair becomes brittle, weak, and crumbly, snapping off right near the scalp like a dry twig. That is why a fungal scalp infection leads directly to noticeable, patchy hair loss! In much rarer instances, this exact same fungus can even wander down to affect the hairs of the eyebrows or eyelashes.
When we doctors examine a scalp in the clinic, we generally divide tinea capitis into two major categories based on how fiercely your body's immune system reacts to the invader:
1. The Non-Inflammatory Type (Black Dot and Gray Patch Scalp Ringworm)
This is the gentler, more classic form of the infection, and thankfully, it rarely leaves permanent scars or lasting baldness. Depending on the specific species of fungus involved, we usually see one of two patterns:
- Black Dot Tinea Capitis: Have you ever looked closely at a bald patch on your child's head and noticed tiny dark specks that look almost like blackheads or freshly shaved stubble? Here, the fungus weakens the inside of the hair shaft so severely that the hair snaps off completely flush with the scalp surface. What gets left behind is the dark tip of the broken hair root sitting inside the follicle, creating that unmistakable "black dot" look.
- Gray Patch Tinea Capitis: In this variation, the fungus coats the outside and inside of the hair shaft, causing the hairs to break off just a few millimeters above the skin. The surrounding scalp gets covered in a fine, dusty, grayish-white scale that looks very much like stubborn dandruff, leaving a dull, circular patch of short, lifeless stubble.
2. The Inflammatory Type (Kerion and Pustular Ringworm)
Sometimes, a child's immune system spots the fungus—especially strains caught from animals or soil—and launches an all-out defensive war against it. While a strong immune response sounds helpful in theory, on the scalp it creates a severe, boggy, painful, pus-filled swelling known medically as a kerion. A kerion looks like a large, raised, angry red abscess or boil that feels soft and spongy when we gently press on it, often oozing yellowish fluid or forming thick honey-colored crusts. Have you ever wondered why we doctors take a kerion so seriously? Because that intense, deep tissue inflammation can actually destroy the delicate hair follicles permanently, leaving behind scar tissue and permanent bald spots (scarring alopecia) if we don't step in quickly to calm it down.
Who Is Most Likely to Get Scalp Ringworm—And Why Does It Target Kids?
If you have several people living in your home, you might be scratching your head wondering why your seven-year-old caught scalp ringworm while you and your teenager haven't developed a single spot. Pretty surprising, right? In clinical practice, we see tinea capitis overwhelmingly in children between 3 and 14 years of age, with the peak age sitting right around elementary or primary school years (ages 3 to 9).
Why are young kids such magnets for scalp fungus while adults usually escape it? It actually comes down to biology and puberty! Once children go through puberty, the oil glands in their scalp (sebaceous glands) start producing higher levels of natural protective fatty acids in their hair oil (sebum). These specific post-puberty fatty acids act like a built-in natural antifungal shield on the scalp, making it much harder for dermatophyte spores to take root. Young children simply don't have those protective scalp oils yet. Plus, think about how kids interact at school, daycare, or sleepovers—heads pressed together looking at a tablet, swapping sports helmets, or tossing winter hats into a shared bin.
That said, adults are not 100% immune. We do occasionally diagnose scalp ringworm in adults—particularly grandparents or parents caring closely for an infected child, older women experiencing hormonal shifts after menopause that change their scalp oils, or anyone living with a weakened immune system (immunocompromise). If your body's natural defenses are lowered due to conditions like poorly controlled diabetes, HIV, cancer treatments (chemotherapy), or long-term steroid medications, the fungus can easily bypass adult defenses. That is also why, whenever one child in a family is diagnosed, we doctors always recommend checking the scalp of every single person living under the same roof—because household members can quietly carry fungal spores on their hair without showing a single itchy spot!
How Common Is This Fungal Scalp Infection Around the World?
If you are feeling isolated or embarrassed that your family is dealing with scalp ringworm, please know that you are in the company of millions of families worldwide. Pediatricians, family doctors, and dermatologists across the United States, the United Kingdom, Canada, and Australia diagnose tinea capitis every single week—making it the single most common fungal infection in children globally.
While children in any neighborhood from London or Toronto to Sydney or Chicago can catch it year-round, these dermatophyte fungi absolutely love warmth and humidity. Because of that biological preference, rates of infection climb noticeably during hot, sweaty summer months, and the condition is even more widespread in tropical and subtropical parts of the world, including regions of Central and South America, Africa, and Southeast Asia. Wherever kids are active, sweating under hats or sports gear, and sharing close spaces, this resilient little fungus finds a welcoming home.
What Are the Symptoms of Scalp Ringworm (Red Scalp, Flaking, and Hair Loss)?
Because scalp ringworm doesn't always form that neat, classic "ring" shape you might see on an arm or leg, parents frequently mistake the early stages for ordinary dry scalp, winter dandruff, eczema, or even psoriasis. Be honest—if you saw a little white flaking on your child's head, your first instinct would probably be to reach for an anti-dandruff shampoo at the pharmacy, wouldn't it? Yet over a couple of weeks, the clues become much more distinct.
Whether the infection sits in one small coin-sized spot or spreads across multiple areas of the head, here are the key warning signs we doctors tell parents to watch for:
- Round or Irregular Patches of Hair Loss (Alopecia): Areas where the hair looks conspicuously thin, stubbly, or completely bald, often expanding slowly outward over weeks.
- A Red, Inflamed, or Swollen Scalp: Underneath the thinning hair, the skin may look pink, angry red, irritated, or noticeably thicker than the normal sleek skin on the rest of the head.
- Stubborn Dry Scales and Dandruff-Like Flaking: Patchy gray or silvery-white flakes that cling tightly to the scalp and hair bases—unlike normal dandruff, which usually dusts the whole scalp evenly without causing hair to snap off.
- Tiny "Black Dots" Where Hair Has Snapped: Little dark pinpoint specks right at the surface of the bald spots, representing broken hair shafts still sitting inside their follicles.
- Relentless Itching (Pruritus): Some children barely itch at all in the first week, while others scratch constantly—especially at night or when their head gets warm—which can accidentally introduce bacteria from under their fingernails into the raw skin.
- Fragile, Brittle Hairs: Hairs right around the border of the patch that feel dull and pull out or snap effortlessly with minimal tension.
- Boggy, Painful Swellings or Pus Bumps (Kerions): In inflammatory cases, small yellow pustules or a larger, tender, raised, crusted mass that oozes fluid and hurts whenever a brush or pillow touches it.
- Tender, Swollen Glands in the Neck (Cervical Lymphadenopathy): Have you felt small, firm, slightly sore lumps right behind your child's ears or down the back of their neck? Don't panic! Those are lymph nodes working overtime to fight off the scalp fungus—a very classic sign of tinea capitis that helps us doctors tell it apart from plain dandruff or autoimmune hair loss.
- Low-Grade Fever and Fatigue: Particularly when the scalp is heavily inflamed or a kerion is forming, your child might feel run-down, cranky, and slightly feverish.
To help you sort through what you are seeing right now on your child's head, take a look at this side-by-side clinical comparison table we use to distinguish the different appearances of scalp ringworm from everyday look-alikes:
| Scalp Appearance or Condition | Clinical Explanation & Next Steps |
|---|---|
| Black Dot Scalp Ringworm (Non-inflammatory Tinea Capitis) |
The fungus invades the inside of the hair shaft (endothrix infection), making the hair so weak that it snaps off right at the level of the scalp surface. This leaves behind flat, scaly bald patches peppered with tiny dark dots that look like blackheads. What you should do: Book an appointment with your Primary Care Physician (PCP) or family GP clinic for a prescription oral antifungal medication; avoid picking or squeezing the black dots. |
| Gray Patch Scalp Ringworm (Non-inflammatory Tinea Capitis) |
Fungal spores coat the outside of the hair shaft (ectothrix infection), causing hairs to break off a few millimeters above the skin. You will see circular patches of short, dull, gray-coated stubble covered in thick, dandruff-like powdery scales. What you should do: Have your family doctor examine the scalp and prescribe a 6-week oral antifungal course paired with a medicated antifungal shampoo to stop the spores from shedding. |
| Inflammatory Kerion (Severe Inflammatory Tinea Capitis) |
An intense immune reaction to the fungus creates a raised, spongy, painful, red swelling studded with pustules or thick yellow crusts. It often mimics a bacterial abscess, causes swollen neck lymph nodes, and carries a real risk of permanent scarring and permanent hair loss. What you should do: See your family GP or visit a local Urgent Care center promptly within 24–48 hours; never try to pop, squeeze, or lance a kerion at home, as it requires urgent oral antifungals and sometimes oral anti-inflammatory steroids. |
| Everyday Dandruff / Seborrheic Dermatitis (Common Non-Fungal Look-Alike) |
Causes diffuse, greasy yellowish or dry white flaking across the scalp without snapping hairs off at the root or creating distinct bald patches. Neck lymph nodes remain completely normal unless the skin is scratched raw. What you should do: Try an over-the-counter medicated dandruff shampoo; however, if you notice even a single patch of broken hairs or baldness, stop guessing and have your doctor check for ringworm. |
| Alopecia Areata (Autoimmune Hair Loss Look-Alike) |
Causes sudden, coin-sized round patches of complete hair loss, but the underlying scalp skin looks completely smooth, pale, and pristine—with zero redness, zero scaling, and no crusty bumps. What you should do: Schedule a routine visit with your family doctor or dermatologist for an accurate diagnosis, as autoimmune hair loss requires completely different treatment than a fungal infection. |
What Causes Scalp Ringworm and What Are the Biggest Risk Factors?
Let's zoom in under the microscope for a moment. As we touched on earlier, tinea capitis is caused by mold-like fungi called dermatophytes. Across North America, the UK, Europe, and Australia, two specific families of dermatophytes are responsible for almost every single case we treat: Trichophyton (especially a species called Trichophyton tonsurans, which is the #1 culprit in the US, UK, and Canada today) and Microsporum (such as Microsporum canis, which is frequently caught from furry pets and remains very common in Australia and parts of Europe).
Now that makes sense why two kids with scalp ringworm might have slightly different-looking rashes, doesn't it? Different species of fungi behave slightly differently on the hair! While any child can encounter these microscopic spores, certain everyday situations make it much easier for the fungus to latch onto the scalp and multiply. Here are the primary risk factors we look for when taking a medical history:
- Age Between 3 and 14 Years: Before puberty kicks in with protective scalp oils, children's hair follicles are naturally much more vulnerable.
- Crowded Group Settings: Spending time in daycares, preschools, elementary classrooms, summer camps, or after-school clubs where dozens of kids share coat hooks, cubbies, and nap mats.
- High-Contact Sports: Does your child wrestle, play rugby, do judo or Brazilian jiu-jitsu, play American football, or swim on a team? Direct head-to-head contact on gym mats or sharing protective headgear and swim caps is one of the fastest ways dermatophytes travel.
- Minor Scalp Cuts, Scrapes, or Tight Hairstyles: Healthy, intact skin is a tough barrier. However, tiny micro-scratches from tight braiding, aggressive brushing, clippers at a barbershop, bug bites, or underlying eczema give fungal spores an open front door right into the skin.
- Warm, Humid Weather and Heavy Sweating (Hyperhidrosis): Fungi thrive in damp, warm microclimates. A child who sweats heavily under a baseball cap, cycle helmet, or winter hat creates the exact greenhouse environment dermatophytes love.
- Sharing Hair Care Items or Headwear: Passing around combs, brushes, hair clippers, barrettes, ribbons, headphones, or hats among friends or siblings.
- Infrequent Hair Washing After Sweating or Contact Sports: Leaving sweat and stray fungal spores sitting on the scalp for days gives the organism extra time to burrow into the hair follicle.
- Weakened Immune Defenses: Living with conditions like diabetes, HIV, or taking immune-suppressing medications makes it much harder for the body to clear fungal spores on contact.
How Does Scalp Ringworm Spread So Easily? (The 3 Main Routes)
Have you ever wondered how your child managed to pick up a fungal scalp infection when nobody else in their friend group seems to have a rash? That is one of the trickiest things about dermatophytes—they are master hitchhikers! We doctors classify the spread of scalp ringworm into three distinct transmission pathways:
1. Person-to-Person Spread (Anthropophilic Fungi)
This is by far the most common way children in cities and suburbs catch scalp ringworm today. When kids put their heads together during play, hug, wrestle, or share a pillow at a sleepover, fungal spores pass directly from one scalp to another. And here is a fascinating medical fact we rarely stop to think about, do we? Some children and adults are what we call asymptomatic carriers. That means they carry live Trichophyton spores on their scalp and shed them onto friends and siblings without ever losing hair or feeling itchy themselves! Unless we treat or use medicated shampoo on household carriers, they can accidentally re-infect your child right after treatment finishes.
2. Animal-to-Person Spread (Zoophilic Fungi)
Has your family recently adopted a new kitten or puppy, visited a petting zoo, or spent time around farm animals, guinea pigs, or rabbits? Animals—especially young kittens, stray cats, and puppies—frequently carry a fungus called Microsporum canis on their fur and skin. Sometimes you will see a telltale patchy, crusty bald spot on the pet's ears, face, or paws, while other times the cat's fur looks completely normal! When a child cuddles the pet against their head or pets the animal and then scratches their own scalp, the fungus hops species. Interestingly, when an animal fungus infects a human scalp, our immune system recognizes it as a "foreign animal invader" and often reacts much more violently, which is why animal-transmitted ringworm is famous for causing those painful, swollen kerions we talked about earlier.
3. Object-to-Person Spread via Contaminated Items (Fomites)
In medicine, we use the word fomites to describe everyday non-living objects that can harbor and pass along infectious germs. Dermatophyte spores are remarkably tough; once they drop off an infected broken hair, they can survive for months—and sometimes over a year—on surfaces! Common culprits include shared hairbrushes, combs, unsterilized barbershop clippers, hats, hoodies, bike or batting helmets, sofa headrests, theater seats, bedsheets, bath towels, and plush stuffed animals. Just think about it for a second: if you spend six weeks curing your child's scalp with medicine, but they keep brushing their hair every morning with the same spore-covered hairbrush, what do you think is going to happen? That's right—the infection starts all over again!
How Do We Doctors Diagnose Tinea Capitis in the Clinic?
If you suspect your child has scalp ringworm, your best first step is scheduling a visit with your Primary Care Physician (PCP) / family GP clinic or pediatrician. Because oral antifungal medications require a multi-week commitment, we doctors want to be completely confident we are treating a true fungal infection rather than eczema, psoriasis, or alopecia areata.
When you sit down with us in the exam room, we start by asking a few friendly detective questions: How long has the spot been there? Is it itchy or tender? Does anyone else at home or school have flaky patches? Have you brought home any new pets recently? Next, we carefully part the hair under a bright light—and often use a handheld lighted magnifying lens called a dermatoscope—to look right down at the hair follicles for telltale "black dots," comma-shaped or corkscrew-shaped broken hairs, and perifollicular scaling. We will also gently feel around the back of the ears and neck to check for those reactive swollen lymph nodes.
What Specific Lab Tests Confirm a Fungal Scalp Infection?
While an experienced doctor can often spot classic scalp ringworm right away during the physical exam, visual inspection alone isn't always 100% foolproof—and international dermatology guidelines strongly encourage confirming the diagnosis with a quick, painless clinic sample before or right as treatment starts. Don't worry: none of these tests involve needles or blood draws! Here are the three main diagnostic tools we use:
1. The KOH Preparation (Potassium Hydroxide Microscopy Test)
To gather a sample, your doctor will gently rub the scaly patch with a moistened cotton swab, a clean toothbrush bristle pad, or the dull edge of a microscope slide to collect a few loose flakes and broken hair stubs. In the lab, a technician places those flakes and hairs onto a glass slide with a drop of a chemical solution called potassium hydroxide (KOH). Why KOH? Because potassium hydroxide dissolves away all the normal human skin cells and debris, leaving only the tough fungal walls (hyphae and spores) shining clearly under the microscope! It is fast, accurate, and often gives us an answer within 24 to 48 hours.
2. Fungal Culture and PCR Testing
Remember how we mentioned that different species of fungi (like Trichophyton versus Microsporum) prefer different habitats? As it turns out, they also respond best to different oral medications! By sending those collected hair stubs or toothbrush brushings to the microbiology lab for a fungal culture, the lab places the sample onto a nutrient dish to see which exact species of fungus grows out. Traditional cultures are the gold standard for accuracy, though fungi grow slowly—so final culture results can take anywhere from 2 to 4 weeks. Many modern clinics in the US, UK, Canada, and Australia now also use faster DNA-based PCR (Polymerase Chain Reaction) swabs, which can pinpoint the exact fungal species in just a few days. Keep in mind: if your child clearly has symptoms of scalp ringworm, we doctors will usually go ahead and start treatment right away so you don't have to wait weeks for the culture to finish growing!
3. Wood's Lamp (Ultraviolet Light) Examination
A Wood's lamp is a specialized handheld blacklight (ultraviolet light) that we shine onto your child's scalp inside a darkened exam room. If the infection is caused by certain species in the Microsporum family (such as the type caught from cats and dogs), the infected hairs will literally glow a bright blue-green or yellowish-green color in the dark! Pretty neat, right? However, it is important to know that the most common human-to-human fungus today (Trichophyton tonsurans) does not glow under a Wood's lamp—so a negative light test doesn't rule out ringworm on its own.
How Is Scalp Ringworm Treated? (Why Oral Medication Is Essential)
Let's talk about the single biggest mistake well-meaning parents make when trying to treat scalp ringworm at home: buying an over-the-counter athlete's foot or ringworm cream (like clotrimazole or hydrocortisone) and rubbing it onto the scalp hoping the spot will go away. Have you already tried doing that? Don't feel bad—almost everyone tries a cream first!
Here is why creams and shampoos alone always fail to cure tinea capitis: topical creams and shampoos only sit on the very top layer of the skin. They physically cannot penetrate deep down to the bottom of the hair follicle bulb where the dermatophyte fungus is hiding and eating the growing hair root. To actually cure scalp ringworm, the medicine has to travel through the bloodstream right into the growing hair root from the inside out. That means prescription oral antifungal medication taken by mouth is mandatory.
1. Prescription Oral Antifungal Medications (The Cure)
Depending on your child's age, weight, and the suspected fungal species, your doctor will prescribe an oral liquid or tablet to be taken daily, typically for 4 to 8 weeks (most commonly around 6 weeks):
- Terbinafine: Often a favorite first-line choice for Trichophyton infections because it concentrates powerfully inside the hair shaft and frequently clears the infection in 4 to 6 weeks. For young kids who cannot swallow pills, tablets can often be crushed into a spoonful of applesauce, chocolate pudding, or peanut butter (always check with your pharmacist first!).
- Griseofulvin: A time-tested liquid or tablet medication used safely in children for decades, and remains the top gold-standard choice when Microsporum (pet-related fungus) is the culprit. It usually requires a 6-to-8-week course. Doctor's pro tip: Griseofulvin absorbs into the body much better when taken right alongside a meal or snack containing healthy fats—like whole milk, yogurt, cheese, peanut butter toast, or ice cream!
- Itraconazole or Fluconazole: Effective alternative oral antifungals that we prescribe for certain stubborn infections, in adults, or when first-line medications aren't ideal.
2. Medicated Antifungal Shampoos (Stopping the Spread)
Now, you might be wondering: "Doctor, if shampoos can't cure scalp ringworm, why did you just hand me a prescription or recommendation for a special shampoo?" Great question! While oral medicine kills the fungus deep inside the root, your child's scalp is still shedding thousands of contagious spores from the surface onto their pillow, classroom chairs, and siblings. Using a medicated antifungal shampoo—specifically one containing selenium sulfide (1% to 2.5%) or ketoconazole (2%)—at least twice a week acts like a containment shield. It washes away and kills surface spores so your child stops being contagious much faster. When using these shampoos, lather it gently onto the scalp and let it sit for a full 5 minutes before rinsing so the active ingredient has time to work. We doctors also frequently recommend having all other family members in the house wash their hair with this medicated shampoo twice a week for a few weeks to clear out any invisible carrier spores!
3. Special Treatment for Painful Kerions (Oral Steroids & Wound Care)
What if your child has developed that painful, swollen, crusted kerion we discussed earlier? In addition to oral antifungal medication, your doctor may prescribe a short course of an oral corticosteroid (such as prednisolone or prednisone) to rapidly calm the explosive inflammation, ease your child's pain, and protect the delicate hair follicles from permanent scarring. Soaking crusty scabs gently with a warm, damp washcloth helps loosen debris cleanly. Note that although a kerion oozes pus and looks exactly like a bacterial boil, it is primarily a fungal hypersensitivity reaction—cutting it open with a scalpel (incision and drainage) actually damages the scalp further and should generally be avoided unless a specialist specifically directs otherwise. Only if a secondary bacterial infection takes hold from scratching will your doctor add an oral antibiotic.
Can My Child Still Go to School or Daycare?
This is always the next question anxious parents ask us! According to infectious disease guidelines from the CDC (United States), the NHS / UK Health Security Agency (UK), the Canadian Paediatric Society, and state health departments in Australia, once your child has officially started their prescribed oral antifungal treatment and medicated shampoo, they generally do not need to miss school or daycare. However, they should avoid high-contact sports (like wrestling) until cleared by their doctor, and must strictly avoid sharing hats, combs, or pillows with classmates.
✔️ What You Should Do & ❌ What to Avoid
- ✔️ DO finish every single dose of the oral antifungal medicine: Even if the redness fades and tiny baby hairs start sprouting at week 3, stopping before the full 6-to-8-week course is finished almost guarantees the fungus will grow right back.
- ✔️ DO give medication with fatty foods if prescribed Griseofulvin: Serving the dose with whole milk, cheddar cheese, avocado, yogurt, or nut butter boosts how much medicine reaches the scalp.
- ✔️ DO replace or disinfect all combs, brushes, and hair clips: Either toss out old cheap combs and buy fresh ones once treatment begins, or soak brushes for 1 hour in a diluted household bleach solution (or hot soapy water) after cleaning out trapped hairs.
- ✔️ DO wash bedding, towels, and hats in hot water: Launder pillowcases, sheets, bath towels, and washable winter hats or baseball caps on a hot cycle and dry them on high heat.
- ✔️ DO have a veterinarian check household pets: If your dog, cat, or guinea pig has any patchy fur loss or crusty skin on its ears or paws, take them to your local vet so they don't keep passing spores back to the family.
- ❌ DON'T shave your child's head: You do not need to shave the hair off to cure scalp ringworm! Shaving causes tiny microscopic razor nicks that actually spread the fungus across the entire scalp and causes unnecessary emotional distress for your child.
- ❌ DON'T rely on over-the-counter creams, coconut oil, tea tree oil, or apple cider vinegar alone: Home remedies and topical pharmacy creams cannot penetrate deep into the hair bulb; delaying prescription oral medication only allows bald patches to grow larger.
- ❌ DON'T ever squeeze, pop, or pick at a swollen kerion: Squeezing an inflamed scalp mass drives fungal debris deeper into the dermis, increases excruciating pain, and greatly raises the risk of permanent scarring hair loss.
- ❌ DON'T share headwear, helmets, headphones, or pillowcases: Keep your child's hair accessories, sports helmets, and towels strictly separate from siblings until their doctor confirms the infection is completely gone.
When Should You Call Your Doctor or Seek Urgent Medical Care?
Most cases of scalp ringworm improve steadily and comfortably at home once oral treatment is underway. However, you should contact your Primary Care Physician (PCP) / family GP clinic or visit a local Urgent Care center promptly if you notice any of these concerning changes:
- A flat scaly spot suddenly puffs up into a soft, spongy, tender swelling (a developing kerion) that oozes pus or yellow fluid.
- The redness around the scalp patch starts spreading rapidly, feeling hot to the touch, or throbbing with pain—which can signal a secondary bacterial skin infection (cellulitis) from scratching with fingernails.
- Your child develops a persistent fever alongside enlarging, very painful swollen lumps in their neck.
- Your child develops a new skin rash elsewhere on their body after starting treatment. (Interestingly, sometimes when oral antifungal medicine starts killing off the scalp fungus, the immune system reacts with an itchy, bumpy rash on the torso or arms called a dermatophytid or "id" reaction—it isn't always a true drug allergy, so never stop the antifungal pills without having your doctor look at the rash first!)
- There is no noticeable improvement after 4 weeks of taking the oral medication faithfully every day.
🚨 When to Seek Immediate Emergency Care (Red-Flag Symptoms)
If you or someone near you develops any of these red-flag symptoms, do not wait — call 911 (US & Canada), 999 or 111 (UK), or 000 (Australia) immediately or go straight to the nearest hospital Emergency Room (ER / A&E):
- Signs of a Severe Allergic Reaction (Anaphylaxis) to Medication: Difficulty breathing, wheezing, shortness of breath, sudden swelling of the lips, tongue, face, or throat, or widespread hives shortly after swallowing an antifungal tablet or liquid.
- Severe Skin Reaction or Blistering: A rapidly spreading red or purple rash that blisters or causes skin peeling, or painful sores inside the mouth, eyes, or lips while taking prescription oral medications.
- Signs of Severe Systemic Infection (Sepsis): A high spiking fever with shaking chills, rapidly spreading fiery red swelling moving down from the scalp onto the forehead or around the eyes, or a child who becomes unusually drowsy, lethargic, confused, or difficult to wake up.
- Signs of Liver Distress While on Oral Antifungals: Severe persistent vomiting, strong upper-right belly pain, dark cola-colored urine, or a noticeable yellowish tint to the skin or the whites of the eyes (jaundice).
💡 Key Take-Home Message
- Scalp ringworm (tinea capitis) is an extremely common childhood fungal infection that burrows into hair follicles, causing red flaky patches, tiny "black dots" of broken hair, and temporary bald spots.
- Because the fungus lives deep inside the hair root, creams and shampoos cannot cure it by themselves—your child needs a full 4-to-8-week course of prescription oral antifungal medication from your family doctor.
- Pair the daily oral medicine with twice-weekly medicated antifungal shampoo (selenium sulfide or ketoconazole), wash hats and pillowcases in hot water, disinfect brushes, and rest assured that once the fungus clears, healthy hair almost always grows right back!





No comments yet. Be the first to share your question or experience below.