
Have you just returned from a prenatal ultrasound or a routine clinic appointment where someone mentioned the word triploidy, leaving you staring at your screen looking for honest, compassionate answers? Or maybe you are trying to make sense of genetic lab results after an unexpected early miscarriage, wondering quietly to yourself, "What went wrong, and did I do something to cause this?" When you are expecting a baby, every scan and blood test carries so much hope, so hearing about a rare chromosome condition feels like the ground has suddenly shifted beneath your feet, doesn't it?
Right now, before we dive into a single medical detail, we doctors want you to pause, let your shoulders drop, and hear the most important clinical truth we tell every parent sitting across from us in the consultation room: triploidy is never your fault. It wasn't caused by that cup of coffee you drank, a stressful week at work, an exercise class, or anything in your family history. In this guide, we are going to walk through everything together step by step—talking plainly about what triploidy is, why a triploid baby receives an extra set of chromosomes, how it affects both the baby and the mother's body, how we confirm a diagnosis, and how we care for your physical and emotional healing.
📌 Key Takeaways at a Glance
- What it is: Triploidy is a rare chromosomal condition where a developing baby has 69 chromosomes (three complete sets) instead of the usual 46 chromosomes (two sets).
- Why it happens: It is a 100% random, accidental biological event that happens at the exact moment of fertilization—most commonly when two sperm fertilize a single egg at the same time (dispermy).
- No parent is to blame: Unlike some genetic conditions, triploidy is not linked to maternal age, diet, medications, or inherited family traits.
- Maternal health matters too: Sometimes triploidy causes an enlarged, cyst-filled placenta (a partial molar pregnancy), which can trigger early high blood pressure (preeclampsia) in the mother and requires close medical follow-up.
- Future hope: Experiencing a pregnancy affected by triploidy is an isolated event; the vast majority of parents go on to have completely healthy pregnancies in the future.
Free pregnancy due date calculator. Enter your last period date or conception date to find your EDD, current trimester, and key milestones.
What Is Triploidy in Pregnancy and How Does a Triploid Baby Happen?
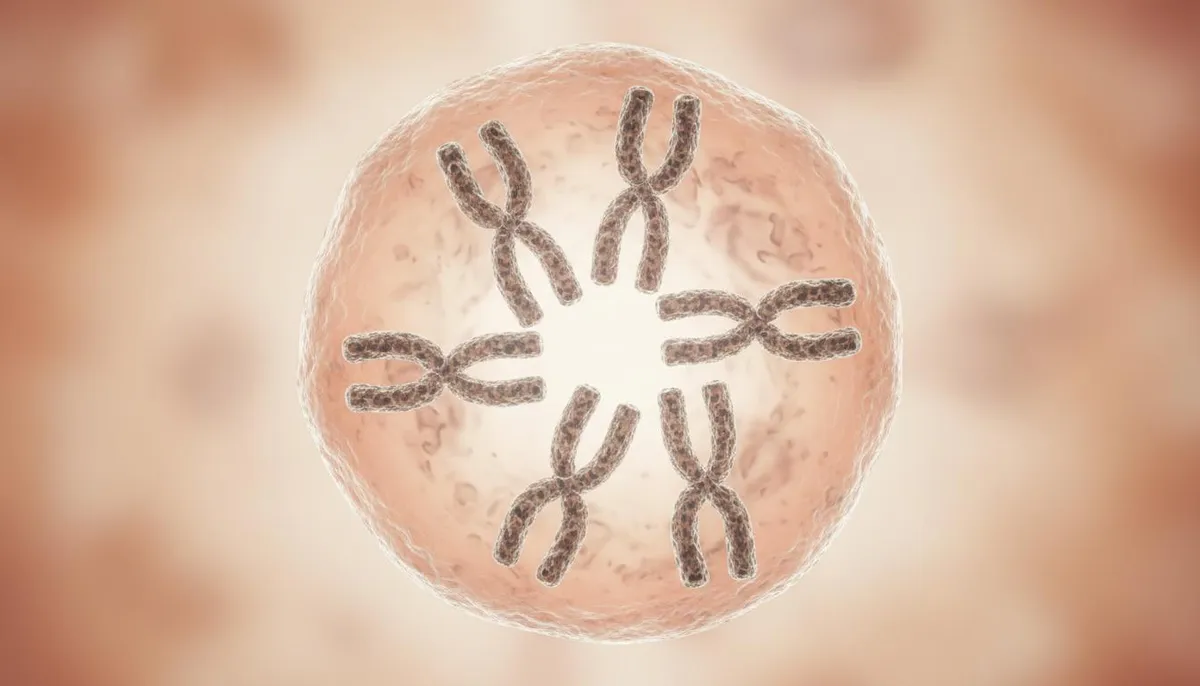
Triploidy is a rare, sporadic chromosomal abnormality in which a fetus inherits three complete sets of chromosomes—totaling 69 chromosomes instead of the normal 46. This extra genetic set occurs randomly at conception when an extra set of 23 chromosomes from either the father or the mother joins the fertilized egg, severely disrupting early fetal and placental development.
To really make sense of how this happens, let's take a quick look at how our body's blueprint normally comes together. Think about it for a second: every healthy cell in your body holds tiny thread-like packages of genetic instructions called chromosomes. Normally, we carry 46 chromosomes arranged in 23 neat pairs—doctors call this normal two-set arrangement being diploid. When a baby is conceived, 23 chromosomes come from the mother's egg and 23 chromosomes come from the father's sperm. When those two sets meet, they add up to 46 chromosomes, giving the developing baby the exact recipe needed to grow peacefully in the womb.
With triploidy, that delicate genetic math changes dramatically. Instead of two sets of 23 chromosomes, three complete sets come together at conception: 23 + 23 + 23 = 69 chromosomes. Have you ever wondered why having more genetic material causes trouble instead of making a baby stronger? Imagine trying to bake a delicate wedding cake, or build a house, when someone hands the builders an extra, competing set of blueprints for every single wall and beam. Cells rely on exact chemical signals to build the heart, brain, kidneys, and placenta. When every cell has 69 chromosomes, those signals clash, making it overwhelmingly difficult for a triploid baby to develop normally inside the uterus.
How Common Is Triploidy in Pregnancies?
You might be surprised to learn how often this actually happens right at the start of conception. We rarely stop to think about how complicated early cell division is, do we? In clinical studies, we doctors see that triploidy actually occurs in roughly 1% to 3% of all recognized conceptions. Pretty surprising, right?
However, the reason most people have never heard the word "triploidy" until a doctor says it to them is that nature has a built-in safety filter early in pregnancy. Over 99% of pregnancies with full triploidy end naturally in a miscarriage during the first or early second trimester—often so early that someone might only notice a heavy, slightly late menstrual period. In fact, when genetic laboratories test tissue from first-trimester miscarriages, triploidy accounts for roughly 15% to 20% of all chromosomally abnormal early pregnancy losses. Very rarely—around 1 in 10,000 live births—a baby with triploidy survives until late pregnancy or birth. Studies also show an interesting biological pattern: more than two-thirds (around 66%) of fetuses identified with triploidy carry male sex chromosomes (69,XXY).
What Causes Triploidy? (Paternal vs. Maternal Origin Explained)
When we sit down with couples after a diagnosis, the very first question they ask—sometimes out loud, and almost always in their hearts—is, "Why did this happen to us?" Let's look at what happens at the microscopic level so you can see clearly why this is a pure roll of biological dice.
Triploidy happens through one of three accidental events right around fertilization:
- Dispermy (Two Sperm Fertilizing One Egg): Normally, the instant a single sperm penetrates an egg, the outer shell of the egg slams shut like an electric gate to keep every other sperm out. Occasionally, two separate sperm cross that barrier at the exact same millisecond before the gate can close. This accounts for about 60% to 66% of all triploidy cases.
- Fertilization by a Diploid Sperm (Abnormal Sperm Division): When the body makes sperm cells through a process called meiosis, a 46-chromosome cell is supposed to split cleanly into 23-chromosome cells. Sometimes a single sperm cell fails to split its chromosomes and carries all 46 chromosomes into a normal 23-chromosome egg.
- Fertilization of a Diploid Egg (Abnormal Egg Division): Just like with sperm, an egg cell can occasionally hold onto an extra set of chromosomes during cell division (a failure of maternal meiosis), carrying 46 chromosomes of its own before being fertilized by a normal 23-chromosome sperm.
Why the Source of the Extra Chromosomes Matters (Diandric vs. Digynic Triploidy)
Now, here is something fascinating that even many parents reading medical pamphlets aren't told right away. Does it make a difference clinically whether that extra set of 23 chromosomes came from the father (sperm) or the mother (egg)? Yes, it makes a huge difference to how the pregnancy behaves on an ultrasound and how it affects the mother's body! Now that makes sense when we look at how genes work, right? Our father's genes push hard to build a large placenta, while our mother's genes focus more on framing the embryo itself.
- Diandric Triploidy (Type I — Extra Set From the Father): When the extra chromosomes come from the father (usually via two sperm), the placenta grows unusually large, thick, and swollen with tiny fluid-filled grape-like sacs. Clinically, this is called a partial molar pregnancy (partial hydatidiform mole). The baby is usually normal-sized or only mildly small early on, though severe structural issues are present.
- Digynic Triploidy (Type II — Extra Set From the Mother): When the extra chromosomes come from the mother's egg, the exact opposite happens. The placenta stays abnormally tiny and thin (without cysts), and the baby experiences severe, early asymmetric growth restriction—meaning the body stays very small while the head looks relatively larger on the ultrasound scan.
What Are the Symptoms and Signs of Triploidy for Both Baby and Mother?
Remember how we talked a moment ago about how triploidy affects both the developing baby and the placenta? Because of that dual impact, we doctors look at two distinct sets of signs: structural signs we see on the baby's ultrasound scan, and physical symptoms the pregnant mother can actually feel in her own body.
Signs That Can Affect the Developing Baby (Ultrasound Findings)
Most of the time, you cannot "feel" fetal signs of triploidy from the outside. Instead, an obstetrician or specialized radiologist spots them during your routine 12-week dating scan or 20-week anatomy ultrasound. Depending on whether the triploidy is paternal or maternal in origin, we may see:
- Early, severe Intrauterine Growth Restriction (IUGR): The baby measures significantly smaller than expected for your due date, often beginning right in the early second trimester.
- Congenital heart defects: Holes between the heart chambers (septal defects) or valve differences that alter how blood pumps through the body.
- Brain and central nervous system changes: Fluid buildup inside the brain cavities (ventriculomegaly or hydrocephalus), incorrect division of the brain hemispheres (holoprosencephaly), or spinal defects like spina bifida.
- Cystic kidney disease and urinary tract differences: Fluid-filled sacs inside the kidneys or low amniotic fluid levels (oligohydramnios) around the baby because the kidneys aren't producing enough fluid.
- Fused fingers and toes (Syndactyly): A classic textbook clue on detailed ultrasound is webbing or fusion specifically between the 3rd and 4th fingers (middle and ring fingers) or toes.
- Abdominal wall and gut differences: Conditions like an omphalocele (where bowel loops sit inside a thin sac at the base of the umbilical cord) or gallbladder and liver variations.
- Distinctive facial features: Wide-spaced eyes (hypertelorism), a cleft lip or cleft palate, low-set ears, a small lower jaw (micrognathia), and a flat nasal bridge.
Signs That Can Affect the Pregnant Mother (Maternal Complications)
Be honest—when we think about fetal chromosome conditions, we usually assume the mother feels just like she would in any normal pregnancy, right? With triploidy, especially the paternal type (partial molar pregnancy) where the placenta grows oversized and cystic, the mother's own health can be directly affected. An abnormal placenta releases skyrocketing levels of pregnancy hormones (hCG) and stress signals into the mother's bloodstream, which can trigger:
- Early-onset Preeclampsia (Toxemia of Pregnancy): Dangerous high blood pressure that shows up much earlier than usual—sometimes before 20 weeks of pregnancy—accompanied by excess protein in the urine (albuminuria).
- Sudden, marked swelling (Edema): Noticeable puffiness in your hands, fingers, face, and around your eyes, rather than just mild ankle swelling at the end of the day.
- Severe, relentless morning sickness (Hyperemesis Gravidarum): Because an enlarged cystic placenta pumps out unusually high levels of the pregnancy hormone hCG, nausea and vomiting can be much more intense.
- Vaginal spotting or dark brown bleeding: Often showing up in the first or early second trimester as the abnormal placenta struggles to stay smoothly attached.
To help you see how these clinical signs connect and what steps we take together, take a look at this comparison guide:
| Clinical Sign or Finding | What It Means & What You Should Do |
|---|---|
| Enlarged Cystic Placenta ("Swiss Cheese" Look on Scan) | Often points toward paternal-origin triploidy (partial molar pregnancy), where the placenta develops fluid-filled clusters alongside fetal tissue. What you should do: Follow up with your obstetrician for genetic confirmation and serial blood tests to monitor your pregnancy hormone (beta-hCG) levels closely. |
| Early Asymmetric Fetal Growth Restriction (Small Body, Normal Head Size) | Commonly seen in maternal-origin triploidy, where a very small, non-cystic placenta cannot supply enough nutrients for the baby's body to grow on schedule. What you should do: Request a referral to a Maternal-Fetal Medicine (MFM) specialist for a high-resolution fetal ultrasound and genetic counseling. |
| Early High Blood Pressure, Facial Swelling & Protein in Urine | Signals early-onset preeclampsia triggered by placental stress—a medical condition that can become dangerous for the mother if left untreated. What you should do: Contact your maternity unit, Primary Care Physician (PCP) / family GP clinic, or hospital labor ward immediately for a blood pressure and urine check. |
| Syndactyly (Fused 3rd & 4th Fingers) + Heart or Brain Differences | A combination of physical markers across multiple organ systems strongly suggests an underlying chromosomal condition like triploidy. What you should do: Discuss diagnostic chromosome testing—such as amniocentesis or chorionic villus sampling (CVS)—with your doctor to get a definitive answer. |
| Vaginal Bleeding & Rhythmic Lower Abdominal Cramping | Indicates that the body may be starting a spontaneous miscarriage, which happens naturally in over 99% of full triploidy pregnancies. What you should do: Call your early pregnancy unit or OB-GYN right away; if bleeding soaks through two thick pads an hour for two hours, go to the nearest Emergency Room (ER / A&E). |
How Do Doctors Diagnose Triploidy? (Screening vs. Diagnostic Tests)
Have you ever wondered why some blood tests in pregnancy only give you a "risk score" while others give a 100% yes-or-no answer? When we doctors investigate possible triploidy, we separate tests into two clear steps: initial screening clues and definitive diagnostic tests.
Step 1: Prenatal Screening Clues
Often, the first hint turns up during your first-trimester combined screening (around 11 to 13 weeks) or a Non-Invasive Prenatal Test (NIPT / cell-free DNA blood draw):
- Detailed Ultrasound Scan: A specialized sonographer or radiologist checks the baby's nuchal translucency (fluid at the back of the neck), organ structures, limb measurements, and placenta appearance.
- Maternal Serum Blood Markers: Hormones like free beta-hCG and PAPP-A can be either sky-high (in paternal triploidy) or unusually low (in maternal triploidy). Sometimes these pattern shifts initially flag as an increased risk for Trisomy 18 or Trisomy 13 before further testing clarifies that all 23 chromosome sets are tripled.
- SNP-based NIPT Blood Tests: While older NIPT blood tests sometimes struggled to pick up triploidy (or came back "inconclusive / low fetal fraction" when the placenta was tiny), newer SNP-based cell-free DNA tests can detect extra parental chromosome sets and flag high suspicion for triploidy.
Step 2: Definitive Diagnostic Confirmation
Because an ultrasound or screening blood test can never be 100% certain on its own, your GP or obstetrician will refer you to a Maternal-Fetal Medicine specialist if you want a concrete diagnosis. Only a diagnostic test that directly counts the chromosomes (a karyotype or microarray) can confirm 69 chromosomes:
- Chorionic Villus Sampling (CVS): Done between 11 and 14 weeks of pregnancy. Using gentle ultrasound guidance, a specialist takes a tiny microscopic sample of placental tissue to count the chromosomes in the lab.
- Amniocentesis: Done from 15 weeks of pregnancy onward. A hair-thin needle guided by ultrasound safely draws a small spoonful of amniotic fluid from the sac around the baby, allowing the lab to examine fetal skin cells directly.
- Post-Loss or Postnatal Genetic Testing: Because so many triploidy pregnancies end in spontaneous early miscarriage, families often find out about triploidy only after their doctor sends pregnancy tissue (products of conception) to the genetics lab. Finding out that your miscarriage happened because of 69 chromosomes often lifts an enormous weight of self-blame off a parent's heart. In rare cases where a baby is born alive, a simple blood draw from the newborn confirms the chromosome count.
Medical Care, Treatment Options, and Why Partial Molar Follow-Up Matters
Talking about medical care when a baby has full triploidy requires extreme gentleness, honesty, and respect for your wishes as parents. Because having 69 chromosomes in every cell is medically incompatible with long-term survival, there is unfortunately no surgery or medication that can remove the extra set of chromosomes or cure the condition.
Depending on when triploidy is diagnosed and how your own health is holding up, your medical team will sit down with you—never rushing you—to talk through three primary care pathways:
- Care During or After a Natural Miscarriage: If the baby's heartbeat stops naturally early in pregnancy, we offer options that fit what feels safest for you physically and emotionally: expectant management (waiting safely at home with pain relief), medical management (tablets to help your uterus pass the pregnancy gently), or a brief hospital procedure (such as a dilation and curettage, or D&C) so tissue can also be checked in the lab.
- Compassionate Perinatal Palliative Care (For Ongoing Pregnancies): If your pregnancy continues into the second or third trimester and your own blood pressure remains safe, many families choose to partner with a perinatal palliative care and neonatal hospice team. Together, we write a birth plan focused purely on warmth, comfort, holding your baby skin-to-skin, making precious memories, and ensuring your newborn never feels pain or distress.
- Active Maternal Protection & Delivery When Mother's Health Is at Risk: Remember how we discussed early-onset severe preeclampsia earlier? If a cystic placenta triggers dangerously high blood pressure, liver strain, or kidney trouble in the mother, continuing the pregnancy can put the mother's life in immediate danger. In those moments, we doctors must recommend ending the pregnancy or delivering early to protect the mother's safety.
A Crucial Clinical Step: Checking if It Was a Partial Molar Pregnancy
Look at what happens here—this is a medical detail you must never skip: if your triploidy pregnancy involved an enlarged, cystic placenta (paternal triploidy / partial molar pregnancy), your doctor will put you on a routine post-pregnancy blood test schedule. Why? Because in a tiny percentage of partial molar pregnancies (less than 1% to 5%), a few active placental cells can linger in the uterus wall after the pregnancy ends—something called Gestational Trophoblastic Neoplasia (GTN). By checking a simple weekly or monthly blood test for the pregnancy hormone beta-hCG until it drops all the way back to zero and stays there, we keep you 100% safe before giving you the green light to try conceiving again.
What to Expect: Life Expectancy and Mosaic Triploidy
We know how deeply parents search the internet looking for stories of babies who beat the odds, so let's talk openly about what the medical records show. In full triploidy—where 100% of the baby's cells carry 69 chromosomes—the vast majority of babies pass away in the womb before birth. Among the very rare infants born alive at term, most pass away peacefully within the first few hours or days of life, while a tiny handful described in medical literature have lived for several months with intensive hospital support.
Wait—what if you have read about an older child living with triploidy? When a baby survives well past infancy, doctors almost always discover a distinct variation called mosaic triploidy (diploid-triploid mosaicism). Think about how mosaic tile art is made out of two different colors of tiles. In mosaic triploidy, only some of the child's cells have 69 chromosomes, while the rest of their cells have the normal 46 chromosomes! Depending on what percentage of cells carry the normal 46 chromosomes, children with mosaic triploidy can live for years or even into adulthood, though they typically need ongoing pediatric support for growth delays, body asymmetry, muscle tone differences, and learning disabilities.
Can Triploidy Be Prevented, and Can You Have a Healthy Baby Next Time?
Can you prevent triploidy with special prenatal vitamins, organic diets, or lifestyle changes? No, triploidy cannot be prevented. Just like we said at the very beginning, you cannot control whether two microscopic sperm reach an egg at the exact same split second. Please let go of any guilt you might be quietly carrying around.
And here is the brightest, most reassuring piece of news we can give you: having one pregnancy affected by triploidy almost never increases your risk for future pregnancies. For the overwhelming majority of couples, the baseline chance of it happening again is virtually the same low random chance as anyone else in the general population (around 1%). Before you start trying again, ask your Primary Care Physician (PCP) or family GP clinic for a referral to a genetic counselor. In the extremely rare case where a couple experiences two molar or triploid pregnancies in a row, genetic specialists can check for rare maternal gene variations (such as NLRP7 or KHDC3L) and guide you through specialized reproductive options like IVF with genetic testing (PGT-A) which can check chromosome numbers before an embryo is ever transferred.
✔️ What You Should Do & ❌ What to Avoid
- ✔️ DO monitor your blood pressure at home or with your GP: If you are currently carrying a pregnancy diagnosed with triploidy, watch out for headaches, vision changes, or sudden swelling in your hands and face, as early preeclampsia can come on quickly.
- ✔️ DO complete every follow-up beta-hCG blood draw: If your pathology report confirms a partial molar pregnancy alongside triploidy, finish all your post-loss blood tests until your doctor confirms your hormone levels are permanently back to zero.
- ✔️ DO nourish and hydrate your body gently during physical recovery: After a miscarriage or delivery, help your body rebuild iron and stamina with familiar, comforting whole foods—like warm oatmeal with berries, leafy green spinach salads, lean roast chicken or salmon, hearty lentil or vegetable soup, and plenty of water or caffeine-free herbal tea.
- ✔️ DO lean on bereavement specialists and pregnancy loss charities: Connecting with specialized groups—like Share Pregnancy & Infant Loss Support or Postpartum Support International (US), the Miscarriage Association or Sands (UK), PAIL Network (Canada), or Red Nose / SANDS (Australia)—connects you with people who truly understand this heartbreak.
- ❌ DON'T blame yourself, your partner, or your daily habits: Working, travelling, exercising, feeling stressed, or having an occasional glass of wine before you knew you were pregnant did NOT cause 69 chromosomes to join together.
- ❌ DON'T rush into trying for another pregnancy before medical clearance: Especially after a partial molar pregnancy, getting pregnant again before your hCG hormone hits zero makes it hard for doctors to tell a healthy new pregnancy apart from lingering molar tissue.
- ❌ DON'T use tampons, douche, or go swimming right after a miscarriage or D&C: While your cervix is still closing and you have any post-loss bleeding, use soft sanitary pads only for 2 weeks to keep bacteria out and prevent uterine infection.
🚨 When to Seek Immediate Emergency Care (Red-Flag Symptoms)
If you or someone near you develops any of these red-flag symptoms, do not wait — call 911 (or 999 in the UK / 000 in Australia) immediately or go straight to the nearest hospital Emergency Room (ER / A&E):
- Heavy vaginal bleeding (Hemorrhage): Soaking completely through two or more thick, full-sized sanitary pads per hour for two hours in a row, or passing blood clots larger than a golf ball or lemon.
- Signs of severe early preeclampsia: A pounding headache that won't go away with paracetamol/acetaminophen, seeing flashing lights or blurry spots in your vision, sudden extreme swelling of your face and hands, or sharp pain right under your ribs on the upper right side.
- Severe, unrelenting pelvic or abdominal pain: Sharp, intense cramping or stabbing pain in your lower belly or shoulder tip that leaves you doubled over or unable to stand straight.
- Dizziness, fainting, or racing heart: Feeling lightheaded when standing up, pale clammy skin, confusion, or shortness of breath.
- Signs of uterine infection after a miscarriage or procedure: A fever over 100.4°F (38°C), shaking chills, or foul-smelling vaginal discharge.
Questions to Ask Your Doctor at Your Next Appointment
When you are sitting in the clinic and emotions are running high, it is completely normal for your mind to go blank the moment the doctor asks, "Do you have any questions for me?" Writing these down on your phone or bringing your partner along to take notes can really help:
- "Did the lab results or ultrasound show whether the extra chromosomes came from the sperm or the egg—and did this involve a partial molar pregnancy?"
- "Do I need serial beta-hCG blood tests over the next few weeks or months, and how long should we wait before trying to conceive again?"
- "If we want to confirm the diagnosis before delivery, what are the benefits and risks of having an amniocentesis or CVS right now?"
- "Am I at increased risk for early preeclampsia right now, and how often should we check my blood pressure and urine?"
- "Can you refer us to a genetic counselor and a local perinatal bereavement counselor who specializes in pregnancy loss?"
💡 Key Take-Home Message
- Triploidy means a baby conceived with three full sets of chromosomes (69 instead of 46)—a purely accidental event at fertilization that no parent can cause or prevent.
- While most triploidy pregnancies result in first-trimester miscarriage, ongoing pregnancies require close blood pressure and placental monitoring to protect the mother from early preeclampsia.
- If triploidy caused a partial molar pregnancy, completing your follow-up beta-hCG hormone checks with your doctor ensures a full, safe physical recovery.
- Take all the time you need to grieve this very real loss, and hold onto the comforting medical truth that your chances of having a healthy baby in your next pregnancy remain remarkably bright.






No comments yet. Be the first to share your question or experience below.