

Every time you speak a sentence, savor a meal, or share a smile, a sophisticated network of mucosal tissues, skeletal scaffolds, sensory receptors, and calcified structures operates in seamless harmony. Yet in routine healthcare conversations, the oral cavity is often relegated to simple cosmetic concerns. In clinical practice, doctors and dentists view the oral cavity as a primary diagnostic window and the physiologic gateway to the entire body. From the biomechanics of mastication to the antimicrobial barrier of saliva, understanding the true architecture of your mouth and teeth is the foundation of lifelong systemic wellness.
Key Clinical Takeaways.
- Dual Dentition: Humans are diphyodonts, developing 20 primary (deciduous) teeth followed by 32 permanent adult teeth engineered for specific mechanical functions.
- Hardest Biological Substance: Dental enamel is the most mineralized tissue in the human body (composed of ~96% hydroxyapatite crystals), but it lacks living cells and cannot regenerate once lost.
- Oral-Systemic Link: Chronic periodontal inflammation and odontogenic infections are established clinical risk factors for cardiovascular disease, poorly controlled diabetes, and adverse pregnancy outcomes.
- Preventive Gold Standard: Twice-daily brushing for two minutes with fluoridated toothpaste, daily interdental cleaning, and regular clinical evaluations prevent the vast majority of dental caries and periodontal destruction.
BMI Calculator
Know your body mass index (BMI) and weight classification
What Is the Functional Anatomy of the Human Oral Cavity?
The oral cavity is lined by specialized oral mucosa, primarily stratified squamous epithelium that acts as a vital mechanical and immunological barrier against pathogens, thermal trauma, and enzymatic degradation. This chamber contains distinct structures that coordinate mastication, deglutition, phonation, and sensory reception.
1. The Palate: Anatomical Partition and Airway Valve.
The roof of the mouth is divided into two distinct anatomical zones:
- Hard Palate (Anterior): Formed by the palatine processes of the maxillae and the horizontal plates of the palatine bones. This rigid osseous ceiling separates the oral cavity from the nasal cavity, providing a sturdy, immovable surface against which the tongue presses food boluses during chewing.
- Soft Palate (Posterior): A mobile fibromuscular fold suspended from the posterior border of the hard palate. During swallowing (deglutition), the soft palate elevates to seal off the nasopharynx, preventing the reflux of food and liquids into the nasal cavity. Hanging from its free inferior border is the uvula, which assists in speech articulation and directs food toward the pharynx. Flanking the soft palate on either side are the palatine tonsils, lymphoid tissues that monitor ingested antigens.
2. The Tongue and Gustatory Neurophysiology.
The tongue is a complex mass of eight intrinsic and extrinsic skeletal muscles innervated primarily by the hypoglossal nerve (CN XII). Its dorsal surface is covered with mucosal projections known as lingual papillae (fungiform, foliate, and circumvallate), which house microscopic taste buds. These specialized sensory receptor cells detect the five primary taste modalities: sweet, salty, sour, bitter, and umami. The tongue continuously manipulates food against the dentition to form a cohesive bolus while playing an indispensable role in acoustic consonant formation.
3. Saliva: The Body’s Natural Chemical Shield.
Saliva is produced continuously by three pairs of major salivary glands (parotid, submandibular, and sublingual) alongside hundreds of minor glands embedded in the mucosa. Adults produce about 0.5 to 1.5 liters of saliva daily. This fluid performs essential clinical functions:
- Chemical Digestion: Contains salivary amylase (ptyalin) to start carbohydrate breakdown and lingual lipase to commence lipid digestion.
- Enamel Remineralization: Supersaturated with calcium and phosphate ions that neutralize oral acids and replenish the crystalline matrix of enamel.
- Immunological Defense: Contains secretory immunoglobulin A (sIgA), lysozymes, and lactoferrin, which inhibit bacterial colonization and biofilm maturation.
How Are Teeth Structured? The Four Vital Dental Tissues.
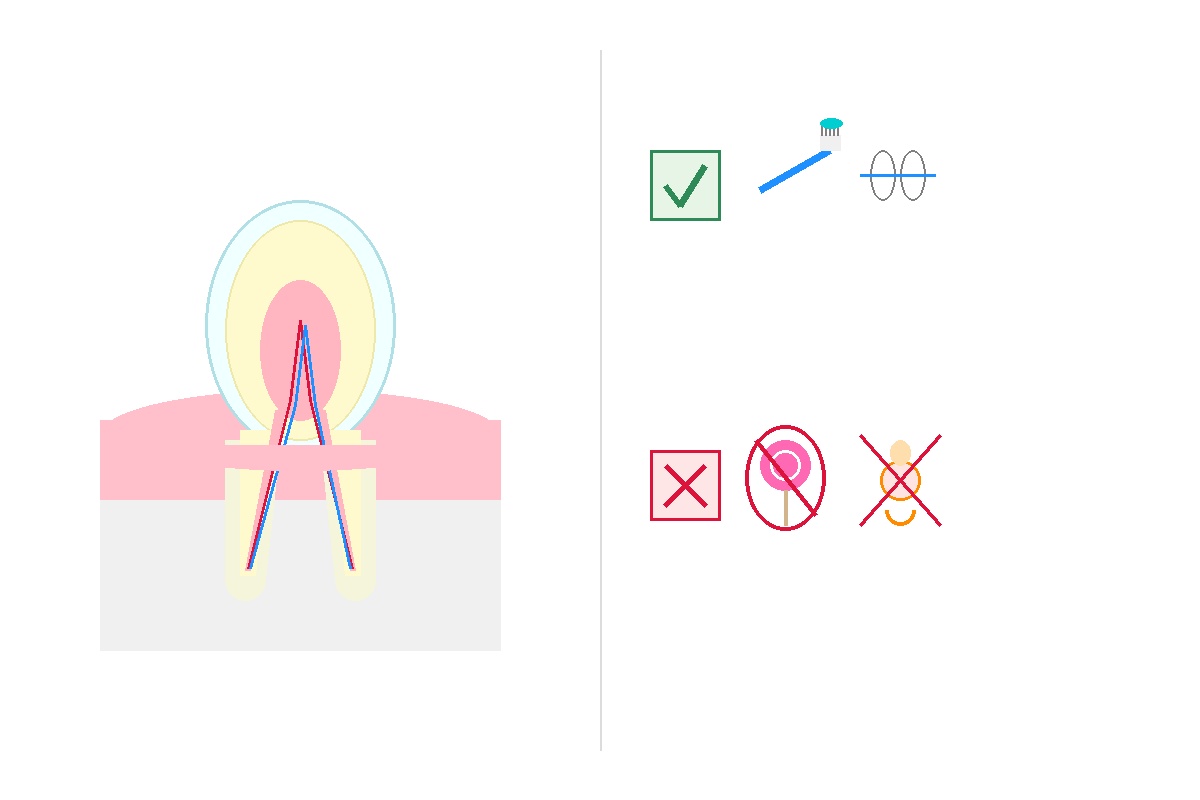
A single tooth consists of two anatomical landmarks: the crown (the visible portion above the gum line) and the root (the anchor embedded within the alveolar bone of the jaw). Histologically, every tooth is composed of four specialized tissues:
- Enamel: The hard, outer translucent layer of the crown. Comprising 96% inorganic minerals (mostly calcium hydroxyapatite), enamel can withstand significant bite forces (exceeding 200–500 N during heavy mastication). Because ameloblasts (enamel-forming cells) are lost upon tooth eruption, damaged enamel cannot cellularly repair itself.
- Dentin: Located beneath the enamel and cementum, dentin forms the bulk of the tooth structure. Composed of about 70% inorganic hydroxyapatite, 20% organic collagen matrix, and 10% water, dentin is slightly more flexible than enamel. It is permeated by millions of microscopic dentinal tubules that transmit thermal and mechanical stimuli to the underlying nerve fibers.
- Dental Pulp: The unmineralized neurovascular core situated within the central pulp chamber and root canals. It contains loose connective tissue, fibroblasts, capillaries, lymphatics, and sensory nerve fibers entering via the apical foramen. The pulp maintains dentin vitality and produces secondary and reparative tertiary dentin in response to trauma or microbial attack.
- Cementum: A specialized, bone-like mineralized tissue covering the anatomical root. It anchors the tooth to the jawbone via collagen bundles known as the periodontal ligament (PDL), providing shock absorption during heavy masticatory loading.

Clinical vitamins and nutritional supplements
Clinically proven high quality vitamins, minerals and immune nutritional supplements.
Check Availability →Types of Teeth and Human Diphyodont Development.
Humans are diphyodonts, meaning they produce two sequential sets of dentition throughout life:
- Primary (Deciduous) Dentition: A set of 20 "baby" teeth that begin calcifying in utero and typically erupt between 6 months and 3 years of age. They maintain spatial integrity within the jawbones to guide permanent successors into position. Exfoliation generally begins around age 6.
- Permanent (Adult) Dentition: A set of 32 teeth that replace the primary teeth and erupt progressively between ages 6 and 21.
Permanent teeth are organized into four specialized quadrants, with each morphological shape optimized for distinct mechanical duties:
- Incisors (8 total): Chisel-shaped front teeth engineered for incising, shearing, and cutting food.
- Canines / Cuspids (4 total): Pointed, long-rooted teeth designed for holding and tearing fibrous foods.
- Premolars / Bicuspids (8 total): Transitional teeth with broad occlusal surfaces bearing two cusps, suited for crushing and pulverizing food boluses.
- Molars (12 total): Large, multi-cusped posterior teeth engineered for heavy grinding. The third molars, commonly referred to as wisdom teeth, are the final teeth to erupt (typically between ages 17 and 25). Due to evolutionary reductions in human jaw dimensions, third molars often become impacted, resulting in pericoronitis, localized cyst formation, or root resorption of adjacent second molars, often necessitating surgical extraction.
Pediatric and Family Oral Health: Evidence-Based Guidelines.
Preventing dental caries (tooth decay) and periodontal inflammation requires consistent, age-appropriate mechanical and chemical hygiene strategies.
| Area of Care. | Evidence-Based Best Practice (Do). | Harmful Habit or Risk (Don't). |
|---|---|---|
| Brushing Technique. | Brush twice daily for a full 2 minutes using fluoridated toothpaste (at least 1,000–1,450 ppm fluoride) and a soft-bristled brush angled at 45 degrees to the gingival margin. | Do not scrub vigorously across teeth with hard bristles, which causes gingival recession and cervical enamel abrasion. Do not right away rinse with water after brushing; spit out excess foam to retain topical fluoride. |
| Interdental Cleaning. | Clean between contact points once daily using dental floss, tape, or interdental brushes as soon as teeth touch. | Do not rely solely on mouthwash to clean interproximal spaces; fluid motion cannot mechanically disrupt sticky bacterial plaque. |
| Pediatric Habits. | Encourage cessation of pacifiers and non-nutritive thumb sucking before age 2–4 to prevent open bites and maxillary crossbites. | Never place an infant to bed with a bottle containing milk, formula, or fruit juice, as pooled carbohydrates trigger rapid Early Childhood Caries (ECC). |
| Diet & Lifestyle. | Limit free sugar intake to less than 5–10% of total energy. Drink fluoridated tap water and encourage custom mouthguards during contact athletics. | Avoid frequent daytime sipping of sugary beverages or citrus infusions, which keeps oral pH below the critical threshold (pH < 5.5) where enamel demineralization accelerates. |
| Environmental Toxins. | Maintain completely smoke-free home and vehicle environments to protect pediatric oral and respiratory health. | Do not expose children to secondhand smoke; epidemiological research directly links passive smoke to higher cavity incidence and compromised immune defenses. |
Emergency Red Flags: When to Seek Immediate Care.
Certain oral presentations represent life-threatening emergencies requiring emergency medical care. Call 911 (US/Canada), 999 (UK), or proceed right away to the nearest Emergency Department (ER / A&E) if you experience:
- Airway Compromise or Stridor: Rapidly spreading floor-of-mouth or submandibular swelling (Ludwig’s angina) that makes breathing, speaking, or swallowing difficult.
- Severe Systemic Sepsis Signs: High fever (> 38.5°C or 101.3°F), confusion, tachycardia, or severe facial cellulitis spreading toward the orbit or eye socket.
- Uncontrolled Hemorrhage: Severe bleeding following dental trauma or surgical extraction that fails to stop after 20–30 minutes of continuous direct pressure.
- Major Facial Skeletal Trauma: Obvious deformity of the jaw, inability to close the teeth together (malocclusion) after blunt impact, or traumatic tooth avulsion alongside suspected head injury.
Authoritative References & Further Reading.
- National Health Service (NHS). Teeth facts and brushing tips. NHS UK, 2024.
- Mayo Clinic Staff. Oral health: A window to your overall health. Mayo Foundation for Medical Education and Research, 2023.
- Centers for Disease Control and Prevention (CDC). Children's Oral Health & Community Water Fluoridation. U.S. Department of Health and Human Services, 2023.
- World Health Organization (WHO). Oral Health Global Report and Action Plan 2023–2030. World Health Organization, Geneva, 2023.


No comments yet. Be the first to share your question or experience below.