

When a 23-year-old university student sat down across from my consultation desk, his hands trembled as he placed his smartphone on the counter. He had spent the preceding night spiraling through online public health registries and epidemiological reports. "Doctor, I read that HIV diagnoses are spiking dramatically among people my age," he admitted, his voice quiet with anxiety. "I had an unprotected encounter weeks ago, and now I can't sleep. Why are numbers climbing when modern medicine is supposed to have solved this?" His distress is far from unique. It mirrors an alarming clinical reality witnessed across acute sexual health clinics worldwide. Despite monumental therapeutic advances, rising HIV infection rates among key demographics continue to challenge modern healthcare systems—primarily because stigma, fear, and misinformation keep people from seeking life-saving prophylaxis and routine screening until severe immunosuppression has already set in.
Key Clinical Takeaways (Medical Summary)
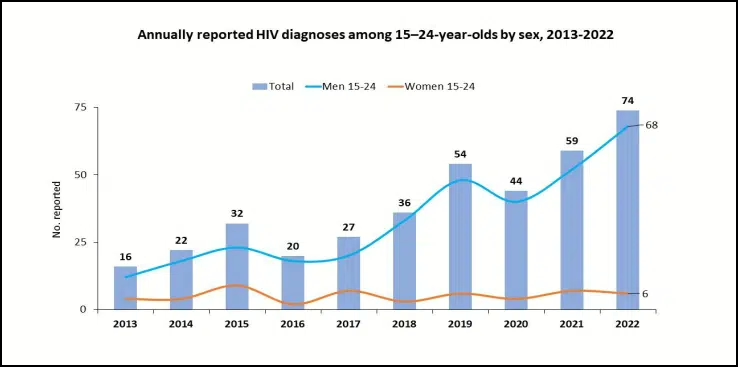
- Surging Diagnoses in Youth: Epidemiological surveillance reveals a sharp upward trend in new HIV cases among youth and young adults aged 15–24, heavily concentrated among men who have sex with men (MSM) due to unaddressed biological and behavioral vulnerabilities.
- The Biological Mechanism: Receptive anal intercourse carries the highest per-act transmission risk (about 1.4% to 1.9%) due to the friable, single-layered columnar epithelium of the rectal mucosa compared to multi-layered squamous genital tissue.
- 99% Prevention via PrEP: Pre-Exposure Prophylaxis (PrEP), taken daily or on demand, reduces the risk of acquiring HIV through sexual contact by about 99%, while Post-Exposure Prophylaxis (PEP) can halt viral integration if initiated within 72 hours of exposure.
- The U=U Paradigm: Effective Antiretroviral Therapy (ART) that suppresses blood plasma HIV-1 RNA below detectable limits (<50 copies/mL or <0.05 × 10⁶ copies/L) completely eliminates sexual transmission (Undetectable = Untransmittable).
Know your body mass index (BMI) and weight classification
Epidemiology: Unpacking the Rise in New HIV Diagnoses.
According to surveillance datasets compiled by global monitoring bodies such as UNAIDS, the World Health Organization (WHO), and national public health agencies, concentrated HIV epidemics are displaying renewed momentum among adolescents and young men aged 15 to 29 years. In numerous urban settings and emerging economies, this demographic constitutes over 12% to 15% of all new annual registrations, with young men who have sex with men (MSM) accounting for an overwhelming majority of sexually acquired infections.
Clinicians observe a troubling diagnostic trend: patients often present to tertiary clinics with late-stage disease, presenting with severely depleted CD4+ T-cell counts below 200 cells/mm³ (0.20 × 10⁹/L). This reveals a prolonged diagnostic latency period spanning several years. Stigma, fear of criminalization or social ostracization, and low awareness of asymptomatic infection prevent timely antibody and antigen screening, transforming preventable early infections into advanced clinical presentations.
how it happens: Viral Transmission and Immune Exhaustion.
1. Biological Susceptibility in Anorectal Intercourse.
The transmission dynamics of the Human Immunodeficiency Virus Type 1 (HIV-1) are strongly governed by tissue histology. Unlike the stratified squamous epithelium lining the vagina or external genitalia, the rectal canal is lined by a delicate, single-cell layer of columnar epithelium. During receptive anal intercourse, shearing forces easily produce micro-abrasions and mucosal tears. This grants HIV direct access to submucosal blood vessels and dense networks of target immune cells, including:
- Dendritic Cells (Langerhans cells): Antigen-presenting cells that inadvertently capture the viral glycoprotein 120 (gp120) and transport it directly to draining regional lymph nodes.
- CD4+ Helper T-Lymphocytes: The primary target host cells possessing both CD4 surface receptors and coreceptors (CCR5 or CXCR4).
- Macrophages: Long-lived reservoirs that harbor replicating virus and evade immune surveillance.
2. The Viral Replication Cycle and CD4 Depletion.
Once inside the host, HIV binds via gp120 to the CD4 receptor, undergoes conformational changes with CCR5/CXCR4 coreceptors, and fuses with the host cell membrane using glycoprotein 41 (gp41). Through the reverse transcriptase enzyme, viral single-stranded RNA is transcribed into double-stranded proviral DNA. Viral integrase then inserts this DNA into the host genome, hijacking cellular transcription machinery to synthesize viral proteins. Immature virions assemble at the membrane and mature via viral protease before budding out, ultimately destroying the host CD4 cell. Over time, without therapeutic suppression, uninhibited viral replication causes systemic immune depletion, leaving the host vulnerable to opportunistic pathogens and malignancies.
Clinical signs: Acute Seroconversion vs. Chronic Latency.
Following exposure, clinical signs progress through distinct body phases:
Acute HIV Infection (Seroconversion Phase).
Occurring 2 to 4 weeks after initial exposure, about 50% to 90% of people experience an acute flu-like illness known as the Acute Retroviral Syndrome (ARS). During this window, viral replication spikes exponentially, and plasma HIV RNA levels often exceed millions of copies/mL, rendering the person exceptionally infectious. Symptoms typically last 1 to 2 weeks and include:
- Sustained high-grade fever and profound rigors .
- Diffuse maculopapular rash, mostly on the trunk, face, and neck .
- Generalized, non-tender lymphadenopathy (swelling in cervical, axillary, and inguinal lymph node chains) .
- Severe pharyngitis, painful mucosal ulcerations of the mouth or genitals, and debilitating myalgias/arthralgias .
Clinical Latency (Chronic HIV Infection).
Following seroconversion, the immune system mounts a partial defense, bringing viral load down to a stable "viral set point." The virus remains actively replicating at low levels, often causing no overt symptoms for 3 to 10 years. Without medical management, CD4+ T-cell levels gradually diminish at an average rate of 50 to 90 cells/mm³ (0.05 to 0.09 × 10⁹/L) per year.
🚨 Emergency Red Flags: When to Seek Immediate Emergency Care
A severely compromised immune system (AIDS stage: CD4 count <200 cells/mm³) exposes the body to rapidly fatal opportunistic infections. Call 911 (US/Canada), 999 (UK), or go to the nearest Emergency Department (ER / A&E) right away if you or an immunocompromised loved one experiences:
- Acute Respiratory Failure: Rapidly progressing shortness of breath, persistent dry cough, and cyanosis (bluish lips or nails), suggesting life-threatening Pneumocystis jirovecii pneumonia (PCP).
- Neurological Emergencies: Sudden confusion, altered mental status, unremitting severe headaches with neck stiffness (nuchal rigidity), visual deficits, or new-onset seizures (indicative of cryptococcal meningitis or cerebral toxoplasmosis).
- Severe digestive Compromise: Inability to swallow fluids (intractable esophageal candidiasis), chronic diarrhea causing severe dehydration, orthostatic hypotension, or delirium.
- Recent Critical Exposure (<72 Hours): If you have experienced potential exposure to HIV through unprotected intercourse or needle sharing within the past 72 hours, report right away to an ER or urgent care clinic to start Post-Exposure Prophylaxis (PEP). Every hour counts.
Diagnostic Standards and Laboratory Benchmarks.
Modern diagnostic protocols rely on high-precision laboratory assays designed to shorten the diagnostic "window period":
- 4th and 5th Generation Antigen/Antibody Immunoassays: These laboratory blood tests detect both HIV-1/2 antibodies and the viral p24 antigen. The p24 antigen emerges in the blood before antibodies are produced, narrowing the detection window to just 18 to 45 days post-exposure.
- Rapid Point-of-Care Antibody Fingerprick Tests: Capable of providing preliminary results in 15 to 20 minutes; window period spans 23 to 90 days. Positive results require mandatory confirmatory lab-based testing.
- HIV-1 Nucleic Acid Testing (NAT / Viral Load PCR): Directly quantifies viral genetic material in blood plasma. Capable of detecting viral particles within 10 to 33 days post-exposure; standard sensitivity reaches down to <20 to 50 copies/mL.
- CD4+ T-Lymphocyte Enumeration: Normal physiological range is about 500 to 1,500 cells/mm³ (0.50 to 1.50 × 10⁹/L). A count below 200 cells/mm³ triggers a clinical diagnosis of Acquired Immunodeficiency Syndrome (AIDS) and mandates urgent antimicrobial prophylaxis for opportunistic pathogens.
Evidence-Based Prevention: PrEP, PEP, and Barrier Methods.
Pre-Exposure Prophylaxis (PrEP).
PrEP is an FDA- and WHO-approved biomedical intervention designed for people who are HIV-negative but at elevated risk of exposure. Available as daily oral regimens (Tenofovir disoproxil fumarate + Emtricitabine [TDF/FTC] or Tenofovir alafenamide + Emtricitabine [TAF/FTC]) or bi-monthly long-acting injectables (Cabotegravir), PrEP prevents incoming viral particles from establishing permanent replication within host cells. Clinical trials (such as the PROUD and IPERGAY trials) show that daily adherence reduces sexual HIV acquisition risk by greater than 99%.
Post-Exposure Prophylaxis (PEP).
PEP is a 28-day emergency medicine-based regimen consisting of three antiretroviral medicines (commonly Tenofovir disoproxil, Emtricitabine, and a potent integrase strand transfer inhibitor such as Dolutegravir or Raltegravir). To be effective, PEP must be initiated within 72 hours of high-risk sexual or occupational exposure, with efficacy dropping precipitously after the first 24 to 48 hours.
Evidence-Based Treatment: Antiretroviral Therapy (ART) and U=U.
The standard of care for every person diagnosed with HIV is immediate initiation of triple-drug Antiretroviral Therapy (ART) regardless of baseline CD4 count. Modern single-tablet once-daily regimens, typically combining two Nucleoside Reverse Transcriptase Inhibitors (NRTIs) with an Integrase Strand Transfer Inhibitor (INSTI), suppress viral replication with minimal toxicity.
The global scientific consensus, validated by monumental cohort studies (including the PARTNER 1 and PARTNER 2 trials encompassing over 76,000 condomless sexual acts), confirms the clinical doctrine of Undetectable = Untransmittable (U=U): when an person maintains an undetectable viral load (<200 copies/mL, with optimal clinical targets below 50 copies/mL) for at least six months, the risk of transmitting HIV to sexual partners is zero.
Best Practices: Comparing Key Interventions.
| ✔️ Medically Recommended Actions (Do). | ❌ Risky Misconceptions & Behaviors (Don't). |
|---|---|
| Undergo voluntary, confidential HIV screening at least once annually if sexually active, or every 3 to 6 months if engaging with multiple partners. | Don't assume the absence of visible symptoms equals absence of infection; asymptomatic clinical latency can last 5 to 10 years. |
| Use water- or silicone-based lubricants with latex or polyurethane condoms to minimize rectal epithelial friction and microscopic mucosal tearing. | Don't use oil-based lubricants (such as petroleum jelly, baby oil, or lotions) with latex condoms, as oil rapidly dissolves and degrades latex integrity. |
| Take Antiretroviral Therapy (ART) exactly at the same scheduled hour every day to prevent developing drug-resistant viral mutations. | Don't rely on PrEP to protect against bacterial sexually transmitted infections (STIs) such as Syphilis, Gonorrhea, or Chlamydia; pair it with condoms. |
| Seek immediate emergency care for PEP within 72 hours of potential exposure; do not wait for symptoms to appear before seeking medical help. | Don't stigmatize or isolate people living with HIV; casual contact, shared cutlery, tears, saliva, and swimming pools do not transmit the virus. |






No comments yet. Be the first to share your question or experience below.