

You are going about your workday when an unmistakable, unrelenting prickle of irritation begins. Within hours, it evolves into an intense, distracting vaginal itch, accompanied by raw redness, burning every time you pass urine, and a thick, clumpy, odorless discharge resembling cottage cheese. For many women, an immediate wave of anxiety follows: Did I catch a sexually transmitted infection? Did I do something wrong with my hygiene? Is this dangerous?
Take a deep breath. In clinical gynecology, these classic symptoms almost universally point to vulvovaginal candidiasis—widely known as a vaginal yeast infection or vaginal thrush. Far from being a reflection of personal cleanliness or an STI, this condition is an extraordinarily common disruption of the delicate vaginal microbiome. Epidemiological data show that roughly 75% of women will experience at least one clinical episode during their reproductive years, and nearly half will navigate recurrent bouts. Understanding why this fungal overgrowth happens is the key to swift, lasting relief.
⚡ Key Clinical Takeaways.
- Not a Sexually Transmitted Infection (STI): Yeast infections stem from an overgrowth of Candida, an opportunistic fungus that naturally resides in the healthy human vaginal canal.
- Hallmark Signs: Unrelenting vulvar pruritus (itching), burning with urination (dysuria), dyspareunia (painful intercourse), and thick, white, odorless curd-like discharge.
- Rapid Targeted Cures: Highly treatable via single-dose oral fluconazole (150 mg) or topical azole pessaries and creams (such as clotrimazole or miconazole).
- Pregnancy Warning: Oral fluconazole is strictly contraindicated during pregnancy due to risks of spontaneous abortion and congenital anomalies; pregnant patients must use doctor-directed topical therapies.
BMI Calculator
Know your body mass index (BMI) and weight classification
What Is a Vaginal Yeast Infection? how it happens and the Vaginal Ecosystem.
A vaginal yeast infection is a form of vaginitis—inflammation of the vaginal mucosa and surrounding vulvar tissue. In roughly 85% to 90% of cases, the causative organism is Candida albicans, a polymorphic, diploid fungus. The remaining fraction is driven by non-albicans species, primarily Candida glabrata, which often exhibits higher resistance to standard first-line azole therapies.
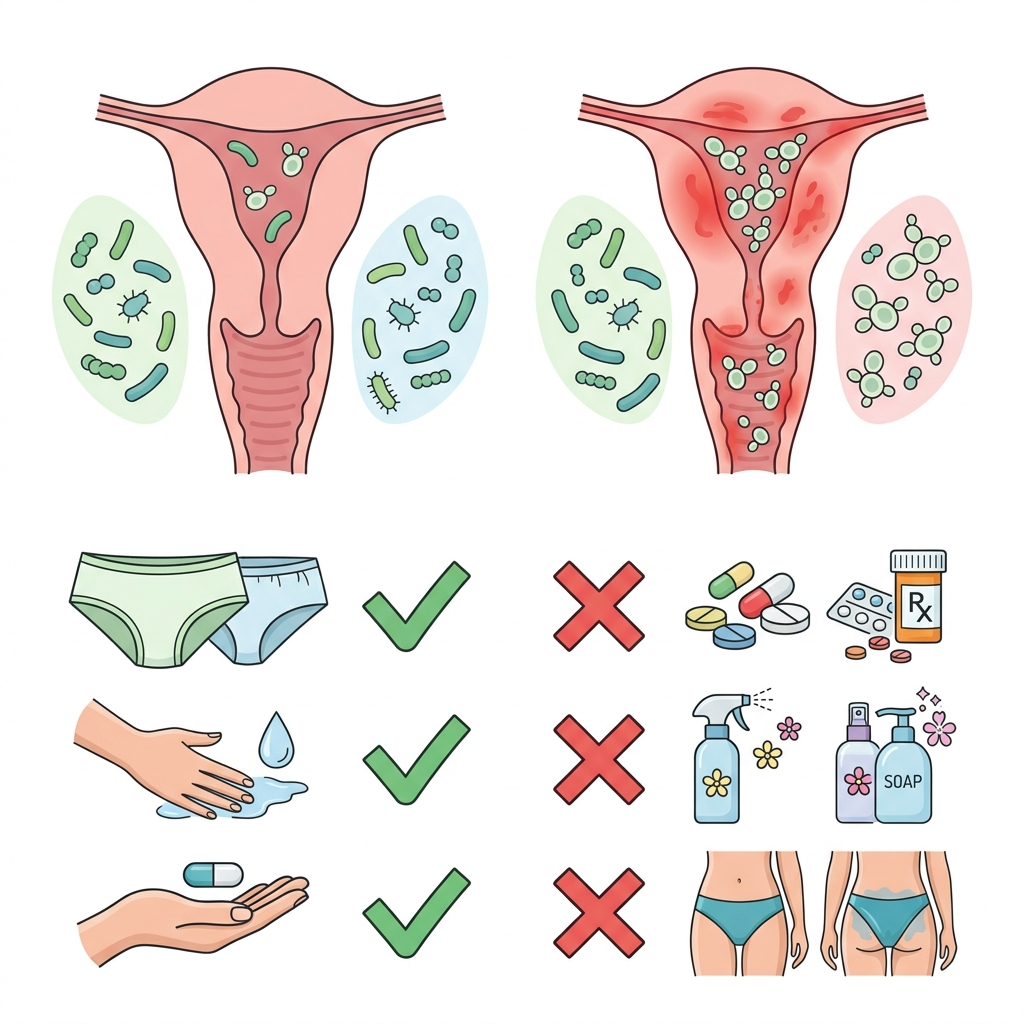
In a healthy vaginal microenvironment, balance is maintained by an ecosystem dominated by hydrogen peroxide- and lactic acid-producing bacteria called Lactobacilli (notably Lactobacillus crispatus and Lactobacillus jensenii). These beneficial microbes ferment glycogen produced by estrogenized epithelial cells into lactic acid, maintaining a protective, naturally acidic vaginal pH between 3.8 and 4.5. This physiological acidity keeps opportunistic yeast dormant as harmless budding blastoconidia.
However, when systemic or localized disruptions suppress the Lactobacillus colony or alter host immunity, Candida switches phenotypic forms: it sprouts invasive elongated filaments called pseudo-hyphae. These penetrate the superficial squamous epithelium, releasing proteases and candidalysin toxins that trigger inflammatory cytokine release, profound tissue edema, and intense neural itching.
Primary Causes and Triggers: Why Does the Balance Shift?
Because Candida already lives commensally on human mucosa, infections are almost never "caught" from an outside surface. Instead, specific systemic triggers allow the fungus to overgrow:
1. Broad-Spectrum Antibiotic Therapy.
Taking oral antibiotics (such as amoxicillin-clavulanate, azithromycin, cephalosporins, or ciprofloxacin) for a completely unrelated condition—like a urinary tract infection, strep throat, or dental issue—eradicates healthy vaginal Lactobacilli alongside bad bacteria. Without competitive bacterial inhibition, Candida multiplies unchecked within 48 to 72 hours of starting the antibiotic course.
2. Elevated Estrogen Levels (Hyperestrogenism).
High circulating estrogen spikes glycogen deposition within vaginal epithelial cells, providing an endless fuel source for fungal proliferation. This is why yeast infections peak during:
- Pregnancy: especially during the second and third trimesters.
- Combined Oral Contraceptives: Especially higher-dose estrogen formulations.
- Hormone Replacement Therapy (HRT): Used in perimenopause and postmenopause.
3. Hyperglycemia and Uncontrolled Diabetes Mellitus.
When serum blood glucose rises above optimal thresholds (e.g., fasting glucose > 126 mg/dL or 7.0 mmol/L; HbA1c > 7.0% or 53 mmol/mol), vaginal secretions become laden with glucose. Fungi thrive in sweet environments. also, hyperglycemia blunts neutrophil phagocytosis, impairing the immune system's local defensive clearance of fungal hyphae.
4. Immunosuppressive Conditions and medicines.
Patients on systemic corticosteroids (such as oral prednisone), calcineurin inhibitors, biologic immunomodulators, chemotherapy, or those living with advanced HIV infection face diminished cell-mediated immunity, paving the way for persistent or recurrent fungal colonization.
5. External Disruptors: Douching and Occlusive Fabrics.
The vagina is entirely self-cleansing. Vaginal douching, using perfumed feminine washes, bubble baths, or scented soaps washes away protective mucosal fluid and kills Lactobacilli. Simultaneously, wearing tight, non-breathable synthetic underwear (such as polyester or nylon) or sitting in damp swimwear creates a warm, humid, hypoxic microclimate where yeast thrives exponentially.
🚨 Critical Warning: Red Flags Requiring Immediate Medical Attention.
While standard uncomplicated yeast infections are not systemic emergencies, certain presentations point toward severe complicated candidiasis, secondary bacterial infections, or dangerous masqueraders like Pelvic Inflammatory Disease (PID). Contact your doctor promptly, call 911 (US/Canada) or 999 (UK), or proceed to the nearest Emergency Department (ER / A&E) if you experience:
- Deep Pelvic or Lower Abdominal Pain: Yeast infections never cause internal uterine or abdominal tenderness. Pain here suggests PID, tubo-ovarian abscess, or acute appendicitis.
- Systemic Signs of Infection: High fever (temperature > 38°C / 100.4°F), shaking chills, nausea, vomiting, or dizziness.
- Malodorous, Discolored Discharge: Strong fishy, foul, or putrid odor, or discharge that appears yellow, greenish, or gray (telltale signs of Bacterial Vaginosis, Trichomoniasis, or Gonorrhea/Chlamydia).
- Severe Tissue Trauma: Extensive vulvar excoriations, painful fissures (skin splits), ulcerations, or blisters (typical of acute primary Genital Herpes).
- High-Risk Patient Profiles: Anyone with active symptoms who is pregnant, severely immunocompromised, or having uncontrolled diabetic ketoacidosis.
Medical test equipment that can be used at home
Essential home medical devices including blood pressure monitors, oximeters and digital thermometers.
Check Availability →Recognizing the Symptoms: Differentiating Vaginal Infections.
Misdiagnosis is extraordinarily common in self-treatment. Up to 60% of women who purchase over-the-counter anti-yeast treatments actually suffer from another condition, such as bacterial vaginosis, trichomoniasis, or contact dermatitis. Review how common vaginal conditions compare:
| Condition. | Discharge Characteristics. | Odor & Vaginal pH. | Predominant Symptoms. |
|---|---|---|---|
| Vaginal Candidiasis (Yeast). | Thick, white, clumpy, curd-like ("cottage cheese"), adhering to vaginal walls. | No odor (or faint yeasty smell); Normal pH (< 4.5). | Intense, maddening pruritus (itching), burning with urination, vulvar redness, dyspareunia. |
| Bacterial Vaginosis (BV). | Thin, homogenous, watery, milky-white to grayish discharge. | Prominent fishy odor (accentuated post-coitus); Elevated pH (> 4.5). | Minimal itching; primarily distress over prominent odor and wetness; no vulvar erythema. |
| Trichomoniasis (STI). | Copious, frothy, thin, greenish-yellow discharge. | Foul, musty, offensive odor; Markedly elevated pH (> 5.4). | Severe inflammation, post-coital bleeding, marked vulvar edema, "strawberry cervix" on exam. |
| Contact Dermatitis. | Normal physiological discharge; clear or off-white. | No odor; Normal pH (3.8 – 4.5). | Severe itching and stinging triggered by a new soap, laundry detergent, lube, or latex condom. |
Clinical Diagnosis: What to Expect at the Doctor's Office.
If your symptoms are recurring, severe, or ambiguous, consult a doctor rather than guessing. An evidence-based diagnostic workup includes:
- Pelvic Speculum Examination: Direct visualization reveals typical erythema, edema of the labia and introitus, and white cottage-cheese-like curd patches adherent to the vaginal vault.
- Vaginal pH Testing: Using narrow-range pH indicator paper. A pH between 4.0 and 4.5 points toward yeast; a pH exceeding 4.5 suggests bacterial vaginosis or trichomoniasis.
- Wet Mount Microscopy (Saline and 10% KOH): Potassium hydroxide (KOH) dissolves cellular debris while leaving fungal cell walls intact, allowing direct visualization of budding yeast cells (blastospores) and branching pseudo-hyphae under a microscope.
- Fungal Culture and NAAT: In cases of Recurrent Vulvovaginal Candidiasis (RVVC)—defined as 4 or more episodes in a 12-month span—a fungal culture or nucleic acid amplification test (NAAT) isolates the specific species (e.g., confirming azole-resistant Candida glabrata or Candida krusei) to guide targeted sensitivity therapy.
Evidence-Based Medical Treatments.
Modern clinical guidelines from the Centers for Disease Control and Prevention (CDC), the British Association for Sexual Health and HIV (BASHH), and the American College of Obstetricians and Gynecologists (ACOG) divide treatment into uncomplicated and complicated categories:
Uncomplicated Infections.
- Oral Therapy (Single-Dose Fluconazole): A single oral dose of Fluconazole 150 mg achieves therapeutic vaginal secretions for up to 72 hours, boasting a clinical cure rate exceeding 90%. It is highly convenient and preferred by non-pregnant patients.
- Topical Azoles (Pessaries and Creams): Available over-the-counter or via prescription. Common regimens include Clotrimazole 1% or 2%, Miconazole 2% or 4%, or Terconazole 0.4% or 0.8%, given intravaginally via pre-filled applicators for 1, 3, or 7 consecutive nights before bed. These are ideal for patients with digestive sensitivity or medicine interactions.
Complicated and Recurrent Infections.
- Dose-Extended Fluconazole: For severe erythema and fissuring, doctors prescribe Fluconazole 150 mg orally every 72 hours for a total of 3 doses (Days 1, 4, and 7).
- Long-Term Maintenance Suppression: For women suffering from chronic recurrent infections, an induction course is followed by a weekly suppressive regimen of Fluconazole 150 mg once weekly for 6 consecutive months.
- Boric Acid Suppositories: For confirmed azole-resistant non-albicans strains (like C. glabrata), intravaginal gelatin capsules containing 600 mg of pharmaceutical-grade Boric Acid inserted once daily at bedtime for 14 to 21 days provide significant fungistatic efficacy. (Warning: Boric acid is fatal if swallowed orally and must never be used during pregnancy).
- Novel Antifungal Agents: New FDA-approved oral glucan-synthase inhibitors like Ibrexafungerp offer non-azole oral alternatives for resistant fungal strains.
Clinical Do's and Don'ts: Protecting Your Microbiome.
Preventing recurrent yeast overgrowth requires preserving the natural physiological defenses of your vaginal flora:
| Do's (Microbiome-Protective Habits). | Don'ts (High-Risk Triggers). |
|---|---|
| Wash Only the External Vulva With Plain Warm Water: The external labia need only gentle water or a mild, unscented soap. Pat dry gently with a clean towel; never scrub. | NEVER Perform Vaginal Douching: Internal douching with vinegar, baking soda, or commercial cleansers strips away Lactobacilli, increasing the rate of fungal and bacterial infections tenfold. |
| Wear 100% Breathable Cotton Underwear: Cotton facilitates natural airflow and absorbs moisture. Consider sleeping without underwear to keep the vulva cool and dry overnight. | Do Not Linger in Damp or Sweaty Activewear: Trapping warm sweat and moisture after intense workouts or swimming accelerates rapid fungal replication. Change right away. |
| Optimize Glycemic Management: If living with diabetes or prediabetes, strict control of your blood glucose removes the sugary fuel source that sustains Candida colonies. | Avoid Inserting Food or Home Remedies: Never insert raw garlic cloves, tea tree oil, or yogurt into the vagina. These cause chemical burns, severe contact dermatitis, and introduce foreign bacteria. |
| Wipe Strictly Front-to-Back: After passing urine or stool, always wipe away from the urethra and vagina toward the anus to prevent transferring enteric pathogens into the vaginal vestibule. | Do Not Rely on Latex Condoms While Using Oil-Based Creams: Many over-the-counter antifungal creams contain mineral oil or petroleum bases that weaken and degrade latex condoms and diaphragms. |


No comments yet. Be the first to share your question or experience below.