

You return from a sunny afternoon stroll through tall grass, a hike in the woods, or garden chores feeling refreshed—until several hours later, when an unbearable, prickling itch flares up around your ankles, waistline, and groin. When you check your skin, you find clusters of angry, fiery red welts that make sleeping or sitting still nearly impossible. Most people assume they were assaulted by mosquitoes or fleas, but the true culprit is often microscopic, virtually invisible, and biologically distinct: the larval harvest mite, universally known as a chigger.
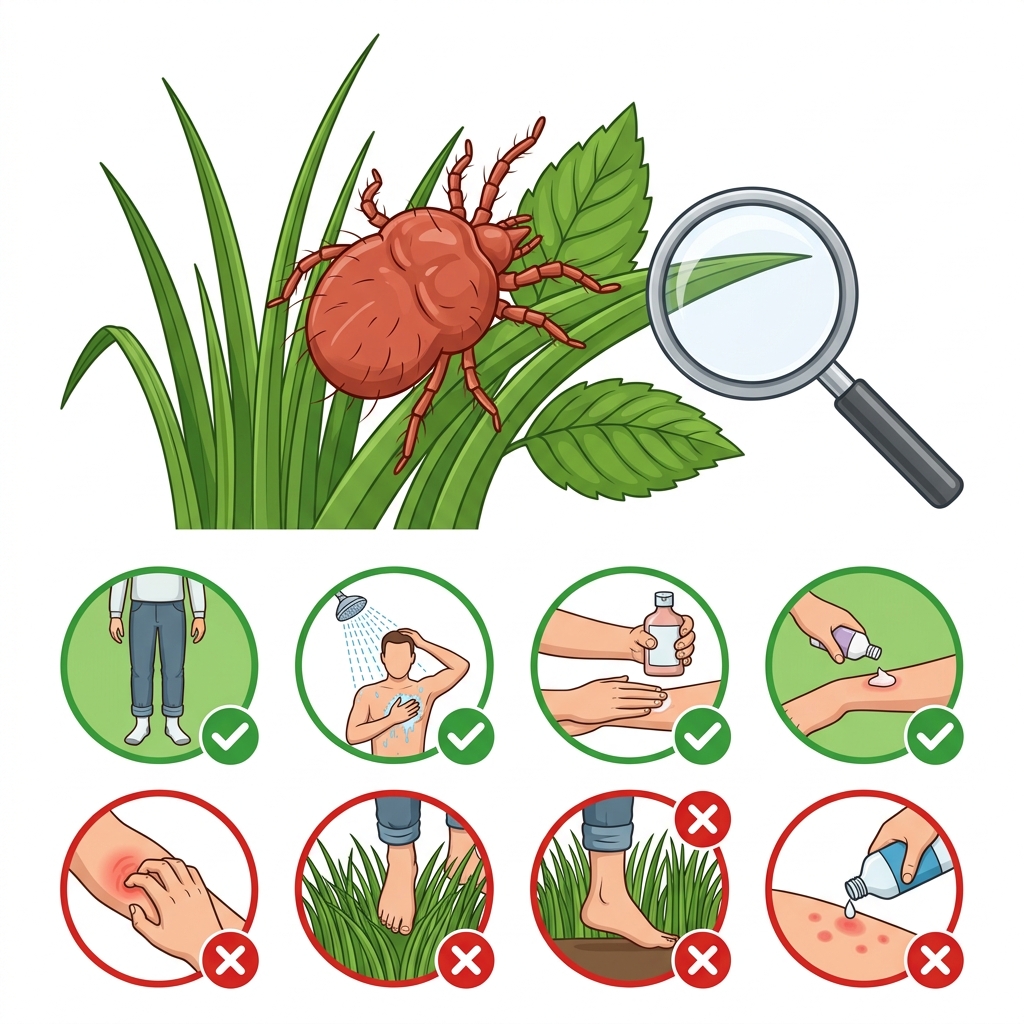
Despite their diminutive size—often smaller than the period at the end of this sentence (under 0.3 millimeters)—chiggers pack a disproportionately fierce punch. Misconceptions surround these microscopic arachnids: they do not burrow beneath your skin, nor do they lay eggs in your tissue. However, the unique enzymatic feeding tube they create triggers an aggressive immune response characterized by intense, lingering pruritus (itching). Understanding the clinical progression of chigger bites enables rapid symptomatic relief and prevents potentially serious secondary skin infections.
Key Clinical Takeaways.
- Microscopic Arachnids, Not Fleas: Chiggers are the six-legged parasitic larvae of mites belonging to the family Trombiculidae. Adults and nymphs feed harmlessly on plant material; only the microscopic larvae bite humans and animals.
- Enzymatic Digestion (No Skin Burrowing): Chiggers do not suck blood or burrow into flesh. They inject specialized proteolytic saliva that dissolves epidermal cells, constructing a rigid feeding straw called a stylostome.
- Delayed Hypersensitivity: Severe itching peaks 24 to 48 hours post-attachment as the host's immune system mounts a vigorous response against foreign salivary proteins.
- Symptomatic First-Line Therapy: Immediate washing with soap and warm water detaches loose mites. Calamine lotion, over-the-counter 1% hydrocortisone cream, and oral non-sedating or nighttime antihistamines relieve discomfort.
BMI Calculator
Know your body mass index (BMI) and weight classification
What Are Chiggers? Identifying the Culprit.
Chiggers—also known scientifically as trombiculid mites, red bugs, or harvest mites—are not insects. They are arachnids related to ticks, spiders, and scorpions. While adult mites possess eight legs and inhabit decomposing plant debris harmlessly, their active larval stage requires protein to mature. Measuring roughly 0.15 to 0.3 mm (visible only as tiny reddish specks under strong magnification), these microscopic larvae perch on the tips of vegetation, waiting for a passing mammal, bird, or human host.
They thrive in humid, damp, and shaded outdoor environments, including:
- Tall grassy fields, overgrown lawns, and pastures .
- Berry patches, dense briars, and woodland edges .
- Riverbanks, lake margins, and damp horticultural soils .
- Harvested agricultural fields (earning them the moniker "harvest mites") .
how it happens: How a Chigger Attacks.
When you brush against infested foliage, chigger larvae swiftly crawl onto your footwear, clothing, or bare skin. They instinctively migrate until they encounter a barrier or area of constriction where clothing fits tightly against warm, delicate skin—such as the tops of socks, tight waistbands, bra lines, the groin, and the armpits.
Once settled, the chigger does not burrow. Instead, it uses specialized piercing mouthparts (chelicerae) to penetrate the superficial stratum corneum, typically selecting a hair follicle or skin pore. The biological mechanism proceeds through distinct phases:
- Proteolytic Injection: The larva injects saliva containing powerful digestive enzymes into the dermis.
- Tissue Liquefaction: These enzymes break down cellular components, liquefying living skin cells into a digestible, protein-rich cellular slurry.
- Stylostome Formation: In response to the caustic enzymes, surrounding host epidermal cells harden and form a microscopic tube-like canal called a stylostome. This rigid structure functions like a drinking straw, allowing the mite to suction up the liquefied host tissue.
- Mite Detachment: After feeding for 2 to 4 days, the fully engorged larva drops off harmlessly to the ground to continue its life cycle. In humans, involuntary scratching or hygiene practices usually dislodge the mite within hours; still, the irritating stylostome and foreign enzymes remain embedded in the skin.
Recognizing the Symptoms: What Do Chigger Bites Look Like?
Because the bite is painless, victims rarely notice the initial attachment. Symptoms develop gradually as the immune system launches an inflammatory response to the salivary enzymes and stylostome:
- Pruritic Papules and Wheals: Within 3 to 6 hours, flat red macules develop, rapidly transitioning into intensely itchy, raised erythematous papules, urticarial wheals, or small fluid-filled vesicles (blisters).
- typical Distribution: Lesions appear in tight clusters or lines along constriction points: ankles, lower legs, behind the knees, around the groin, waistline, and axillae (armpits).
- Peak Pruritus: Itching typically reaches its peak intensity 24 to 48 hours after exposure, often disrupting sleep and normal concentration.
- Prolonged Resolution: While the mite is gone, the embedded stylostome takes time to degrade. Complete skin healing generally takes 1 to 2 weeks, with residual hyperpigmentation (discoloration) lasting several weeks in some skin types.
- Summer Penile Syndrome: In young boys, bites occurring on the penis or scrotum can trigger substantial edema, severe pruritus, erythema, and dysuria (painful urination). While alarming to parents, this acute hypersensitivity reaction is benign and resolves with proper pediatric care.
Emergency Red Flags: When to Seek Immediate Care.
While common chigger bites are benign, secondary bacterial infections from aggressive scratching or rare systemic allergic reactions can become life-threatening. Seek urgent emergency services or proceed right away to the nearest Emergency Department (ER / A&E) if you experience:
- Signs of Severe Anaphylaxis: Rapid onset of facial swelling, lip or tongue angioedema, difficulty swallowing, wheezing, shortness of breath, severe dizziness, or a feeling of throat closure. right away call 911 (US/Canada) or 999 (UK).
- Spreading Cellulitis: Rapidly expanding redness (erythema extending several centimeters away from the bite site), intense localized heat, marked swelling, and severe pain to the touch.
- Systemic Signs of Sepsis: High fever (temperature > 38.3°C / 101°F), rigors, chills, rapid heart rate, confusion, or red streaks extending along lymphatic channels toward the trunk.
- Severe Urinary Obstruction: Inability of a child to pass urine due to marked genital swelling associated with Summer Penile Syndrome.
Clinical Diagnosis: Differentiating Chigger Bites.
Diagnosis is primarily clinical, based on a complete medical history and physical examination. doctors look for the hallmark grouped papules along areas of tight clothing following recent outdoor exposure to grassy or wooded areas. Laboratory testing or skin biopsies are rarely indicated unless atypical presentation warrants ruling out other dermatologic conditions:
- Scabies (Sarcoptes scabiei): Unlike chiggers, scabies mites burrow beneath the stratum corneum, creating linear tracks in webbed finger spaces, wrists, and elbows. Scabies is contagious and does not resolve without prescription scabicides.
- Flea and Bedbug Bites: Flea bites concentrate mostly on the feet and lower legs without preference for clothing bands. Bedbug bites often exhibit a classic "breakfast, lunch, and dinner" linear triad and originate from indoor sleep settings.
- Tick Bites: Ticks remain firmly attached to host skin for days, expanding noticeably; certain species carry Lyme disease, presenting with an expanding annular erythema migrans ("bull's-eye") rash.
Evidence-Based Medical Treatment and Home Management.
Because trombiculid mites in North America, Europe, and many parts of the globe do not transmit pathogens to humans (unlike species in parts of rural Asia that can transmit scrub typhus), treatment focuses strictly on symptom relief and preventing secondary bacterial invasion.
| Intervention. | Clinical Mechanism. | Application & Instructions. |
|---|---|---|
| Immediate Soap & Water Wash. | Mechanical removal of unattached or loosely attached crawling larvae. | Take a warm shower or bath right away upon returning from outdoors; vigorously lather with a washcloth. |
| Cold Compresses. | Vasoconstriction and blunting of localized cutaneous nerve endings to decrease itch transmission. | Apply an ice pack wrapped in a clean cloth or a cold washcloth for 10 to 15 minutes every 2 to 3 hours as needed. |
| Topical Antipruritics (Calamine / Pramoxine). | Mild astringent and soothing surface anesthetic properties. | Apply calamine lotion or pramoxine-based preparations sparingly over clean, dry skin 3 to 4 times daily. |
| Topical Corticosteroids (Hydrocortisone 1%). | Downregulation of inflammatory cytokines and reduction of mast-cell mediated swelling. | Apply a thin layer of over-the-counter 1% hydrocortisone twice daily. For severe cases, a doctor may prescribe high-potency topical steroids. |
| Oral Antihistamines. | H1 receptor antagonism reduces central and peripheral pruritic stimulation. | Daytime: Second-generation non-sedating agents (cetirizine, loratadine). Nighttime: Diphenhydramine or chlorpheniramine to facilitate restful sleep. |
The Critical Imperative: Do Not Scratch.
The single greatest clinical risk associated with chigger bites is excoriation from fingernails, which breaches the protective cutaneous barrier and introduces opportunistic bacteria such as Staphylococcus aureus and Streptococcus pyogenes. This can trigger secondary infections:
- Impetigo: Superficial bacterial infection presenting with fragile vesicles that rupture, leaving behind classic honey-colored, crusty lesions requiring topical mupirocin or oral antibiotics.
- Cellulitis: Deeper dermis and subcutaneous tissue infection characterized by expanding erythema, marked induration, and warmth requiring prescription systemic antibiotics.
Proven Prevention Strategies: How to Protect Yourself.
Preventing chigger bites is far simpler than soothing the persistent itch once an infestation occurs. Implement these evidence-based barrier and repellent techniques whenever venturing outdoors:
| Recommended Do's. | Harmful Don'ts. |
|---|---|
| Apply EPA-Registered Repellents: Use insect repellents containing 20% to 30% DEET, Picaridin, or Oil of Lemon Eucalyptus (OLE) onto exposed skin and clothing edges. | Do Not Apply Nail Polish or Bleach: Debunk the pervasive myth that chiggers live inside the skin; applying clear polish, rubbing alcohol, kerosene, or bleach only causes chemical burns and severe contact dermatitis. |
| Treat Fabrics with Permethrin: Spray clothing, socks, and hiking boots with 0.5% permethrin spray, letting it dry completely before wearing. Permethrin kills mites on contact. | Do Not Walk Through High Brush Barefoot: Avoid wearing shorts, sandals, or loose-fitting clothing when traversing unmaintained vegetation or damp lakeside grass. |
| Tuck Pants into Socks: Create a physical barrier by tucking long pant legs securely into tightly woven socks or hiking gaiters to prevent mites from reaching bare skin. | Do Not Leave Dirty Clothes in Living Areas: Avoid tossing outdoor garments on beds or couches; wandering mites can transfer to family members or bite hours later. |
| Wash Gear right away in Hot Water: Wash outdoor clothes in hot water (> 54°C / 130°F) and dry on high heat for at least 30 minutes to eradicate any lingering mites. | Do Not Give Unsupervised Adult medicines to Children: Never give sedating antihistamines or adult topical preparations to infants or young children without pediatrician guidance. |





No comments yet. Be the first to share your question or experience below.