
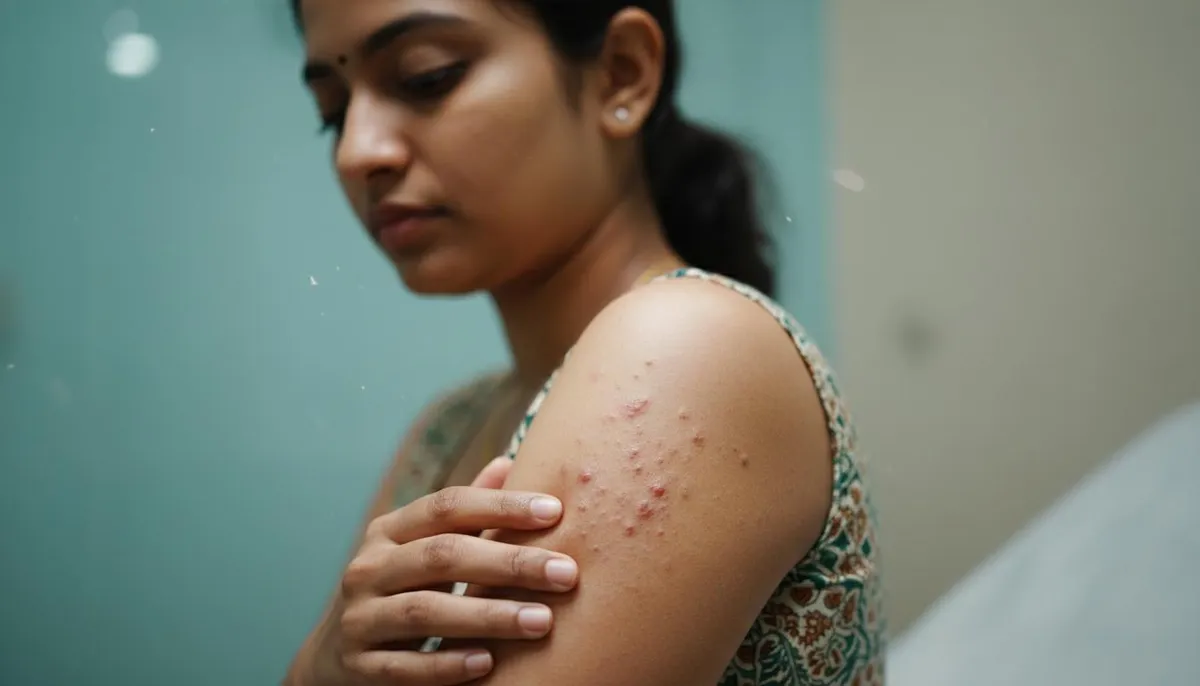
Have you ever bought a gritty walnut scrub or a stiff loofah sponge, hoping you could simply scrub away those stubborn, sandpaper-like bumps on the backs of your arms? Be honest, you have tried doing this in the shower too, haven't you? It is easily one of the biggest misconceptions out there. Many people assume that bumpy "chicken skin" comes from clogged pores caused by sweat or poor hygiene, leading them to scrub harder and harder until their skin turns raw and angry. When patients ask us doctors about the real causes of keratosis pilaris, they are often relieved to learn that this roughness has nothing to do with how clean you are. Instead, it is a completely harmless, inherited way your skin handles a natural protein called keratin. Once you stop fighting your skin with rough brushes and start working with its natural biology, smoothing out those tiny bumps becomes so much easier.
📌 Key Takeaways at a Glance
- Completely Harmless: Keratosis pilaris ("chicken skin") is a benign, non-contagious genetic skin trait that never turns into a serious internal illness.
- The Real Root Cause: The primary causes of keratosis pilaris involve a harmless buildup of keratin protein and dead skin cells that form tiny plugs inside your hair follicles.
- Ditch the Scrubs: Aggressive physical scrubbing, dry brushing, or picking at the bumps only triggers more redness, irritation, and dark marks.
- Smart Daily Care: Gentle chemical exfoliants (topical keratolytics) like urea, lactic acid, or salicylic acid paired with rich ceramide moisturizers smooth the skin safely.
- Natural Improvement: While flare-ups are common during dry winter weather, the bumps often fade and calm down naturally as you get older.

What Is Keratosis Pilaris and What Are the Causes of Keratosis Pilaris?
The primary causes of keratosis pilaris are genetic variations in skin cell turnover that make excess keratin—a natural protective skin protein—build up and plug hair follicles, often triggered or worsened by dry skin, eczema (atopic dermatitis), hormonal shifts, and low winter humidity.
Let's look at what happens right beneath the surface of your skin. Normally, your outer skin cells mature, rise to the top, and flake off effortlessly in the shower or on your clothes without you ever noticing. We rarely stop to think about that constant renewal, do we? However, if you have keratosis pilaris (clinically known as follicular hyperkeratosis), that microscopic shedding conveyor belt gets a little sticky.
Instead of sloughing off evenly, excess keratin clumps together with dead skin cells and forms tiny, hard plugs right inside the openings of your hair follicles. Think about it for a second: when a microscopic plug blocks the exit, the fine body hair (vellus hair) growing underneath gets coiled and trapped right inside the bump. At the same time, tiny blood vessels wrapping around that blocked follicle can widen slightly, creating a faint pink or reddish ring around the bump. Pretty surprising, right?
Studies from major dermatology clinics across the United States, the UK, Canada, and Australia show that keratosis pilaris affects roughly 50% to 80% of teenagers and about 40% of adults. You cannot catch it from sharing towels, swimming pools, or gym equipment, and you cannot pass it to anyone else through touch.
What Are the Underlying Causes and Risk Factors for Keratosis Pilaris?
Have you ever wondered why one person in a household has completely smooth arms while their sibling or child has rough, goosebump-like skin year-round? When we doctors examine the exact what causes keratosis pilaris puzzle in our family clinics, we look at four main biological and environmental triggers that work together.
- Family Genetics and Filaggrin Mutations: Genetics sits right at the top of the list of pilaris keratosis causes. It follows what we call an autosomal dominant pattern, meaning if just one parent has keratosis pilaris, each child has roughly a 50% chance of inheriting it. Many people with these bumps carry a tiny variation in their filaggrin gene—the exact blueprint your body uses to build a strong, moisture-locking skin barrier.
- Dry Skin and Eczema Connections: If you or your family members deal with dry skin, seasonal hay fever, asthma, or eczema (atopic dermatitis), your skin barrier naturally loses water faster than average. Up to a third of people with eczema also develop keratosis pilaris because a thirsty skin barrier plugs up much more easily.
- Hormonal Fluctuations: Have you noticed how these bumps often show up right as kids hit their pre-teen years, or suddenly flare during pregnancy? Shifts in hormones directly influence how quickly your follicular cells turn over and how your natural skin oils behave.
- Acquired Keratosis Pilaris and Medical Links: While most cases start in childhood, what if bumps appear suddenly in adulthood? We doctors call this acquired keratosis pilaris. It can occasionally show up alongside metabolic shifts like insulin resistance, higher body weight, hypothyroidism, or after starting certain targeted medications. Rarely, severe nutritional gaps—such as a lack of fat-soluble Vitamin A (phrynoderma) or Vitamin C—can mimic these follicular bumps if someone follows an extremely restricted diet.
How Do You Recognize the Signs and Where Do Bumps Appear?
What do you think when you run your fingers across an affected patch of skin? Most patients tell us it feels just like fine-grit sandpaper, unglazed pottery, or permanent goosebumps that never flatten out, even when you are warm. Each tiny bump (follicular papule) measures only about 1 to 2 millimeters across. Sometimes they feel slightly dry or mildly itchy, especially after taking off tight winter sweaters or leggings.
Common Anatomical Sites: Arms, Thighs, Back, and Cheeks
Where do these tiny keratin plugs prefer to settle? While they can technically appear anywhere you have hair follicles (which means never on the palms of your hands or soles of your feet), they have very distinct favorite spots:
- Outer and Back of the Upper Arms: By far the most classic spot. Almost everyone with keratosis pilaris notices it here first.
- Front and Sides of the Thighs and Buttocks: Very common in both children and adults, often worsened by friction from snug jeans or athletic wear.
- Upper Back and Shoulders: Many patients come in worried about stubborn bumps on their back, assuming it is body acne, when it is actually uniform keratin plugging.
- Keratosis Pilaris in Children and Facial Cheeks (Keratosis Pilaris Rubra Faceii): In babies, toddlers, and school-aged kids, bumps frequently dust the outer cheeks and eyebrows. A specific subtype called keratosis pilaris rubra faceii causes persistent rosy-red cheeks dotted with tiny pinpoint bumps. Parents often mistake these facial bumps for baby acne, milia (tiny white cysts), or childhood rosacea.
Color Variations Across Skin Tones and Seasonal Patterns
Keratosis pilaris does not look identical on everyone. On fair or light complexions, the bumps usually look white, pink, or bright red, surrounded by a blush-colored halo (keratosis pilaris rubra). On medium, olive, brown, or deep skin tones, inflammation shows up differently—the bumps often look tan, warm brown, plum, or slate-gray (keratosis pilaris alba or hyperpigmented KP). If you scratch or pick at them, they easily leave behind stubborn dark marks (post-inflammatory hyperpigmentation) that take months to fade.
Remember how we talked about the skin barrier earlier? That explains why keratosis pilaris follows a predictable calendar. During the crisp, freezing months of winter—when outdoor humidity drops and indoor central heating runs nonstop—your skin loses moisture rapidly, making the bumps feel much sharper and rougher. Once warm, humid summer air arrives, the bumps often soften up on their own. Now that makes sense, right?
How Is Keratosis Pilaris Diagnosed by Your Doctor?
Be honest, you have probably zoomed in on your arms under the bathroom light and searched online to see if you need a special lab test, haven't you? Here is some great news: diagnosing keratosis pilaris is quick, painless, and straightforward. When you visit your Primary Care Physician (PCP) or family GP clinic, we doctors can almost always diagnose it simply by looking closely at your skin and gently feeling the texture.
You almost never need blood tests, bacterial swabs, or a skin biopsy. Sometimes we hold a small lighted magnifying lens called a dermatoscope against your arm, which lets us see the tiny coiled hair trapped right inside the keratin plug. Just as importantly, we make sure your bumps aren't caused by a lookalike skin condition that needs different medication.
| Skin Condition / Lookalike | How We Doctors Tell Them Apart & What You Should Do |
|---|---|
| Keratosis Pilaris ("Chicken Skin") | Uniform, tiny 1–2 mm painless bumps that feel like dry sandpaper, mostly on the outer upper arms, front of thighs, buttocks, or children's cheeks. What you should do: Use daily lukewarm showers, gentle chemical exfoliant creams (urea or lactic acid), and rich ceramide moisturizers while skin is still damp. |
| Folliculitis (Infected Hair Follicles) | Tender, itchy, or painful red bumps often topped with tiny yellow pus-filled heads, triggered by sweat, hot tubs, shaving, or tight gym clothes. What you should do: Avoid squeezing the bumps, wash with a gentle antiseptic cleanser, and see your family GP clinic if you need a targeted antibacterial or antifungal wash. |
| Acne Vulgaris & Milia | Acne features mixed blackheads, whiteheads, oily skin, and deeper tender cysts on the face, chest, and upper back; milia are tiny, smooth, pearl-like white cysts without rough follicular plugs. What you should do: Use non-comedogenic cleansers and salicylic acid or adapalene products, or ask your doctor about safe office extraction for stubborn facial milia. |
| Atopic Dermatitis (Follicular Eczema) | Intensely itchy, dry, scaly patches where small bumps cluster together and flare up with scratching, allergies, or harsh soaps. What you should do: Apply thick, fragrance-free emollient ointments several times a day and talk to your PCP about a short course of mild prescription anti-inflammatory cream. |
What Is the Best Keratosis Pilaris Treatment and Daily Skincare Strategy?
Because the underlying causes of keratosis pilaris are rooted in your genetic blueprint, there is no one-time pill that permanently changes how your skin makes keratin. But don't let that discourage you! With a smart, consistent three-step home routine, you can dissolve the plugs, calm the redness, and keep your skin feeling remarkably smooth. Let's walk through what actually works.
1. Topical Keratolytics (Gentle Chemical Exfoliants)
Instead of scraping the tops of the bumps off with a rough pumice stone or body brush, we doctors recommend chemical exfoliants—medically called topical keratolytics. Look at what happens here: these gentle lotions dissolve the microscopic "glue" holding dead keratin plugs together so they melt away without scratching your skin.
- Urea Creams (10% to 20%): A superstar ingredient available over the counter at your local pharmacy. Urea does double duty by gently breaking down thick keratin plugs while pulling deep moisture right into the outer skin layer.
- Lactic Acid or Ammonium Lactate (5% to 12%) & Glycolic Acid: These alpha-hydroxy acids (AHAs) gently loosen dead surface cells and boost skin hydration. They are terrific for dry arms and legs.
- Salicylic Acid (0.5% to 2%): Because salicylic acid is a beta-hydroxy acid (BHA) that dissolves in oil, it slips right down inside the hair follicle to clear out trapped debris. It is especially helpful if you have bumps on your back or thighs.
- Gentle Topical Retinoids or Azelaic Acid: If over-the-counter lotions aren't enough after 6 to 8 weeks, your family GP or dermatologist may suggest a mild topical retinoid (like adapalene) or azelaic acid cream to regulate how quickly your follicle cells turn over. For young children or sensitive facial cheeks (keratosis pilaris rubra faceii), always skip strong acids and stick to mild moisturizing creams or doctor-approved gentle formulations.
2. Deep Hydration and the "Soak-and-Seal" Method
Do you recall what we mentioned at the very beginning about a dry skin barrier making plugs worse? Softening the skin barrier is half the battle. Choose thick, fragrance-free creams or ointments rich in ceramides, petrolatum, dimethicone, glycerin, or shea butter—especially if you are dealing with dry, itchy skin alongside your bumps.
Here is a simple doctor trick that changes everything: apply your moisturizer within three minutes of stepping out of the shower while your skin is still slightly damp. Gently pat (don't rub!) your skin with a soft towel and smooth the cream right on. Locking in that surface water right after a bath makes complete sense, right?
3. Smart Bathing Habits and Home Humidity
Long, steaming-hot showers feel wonderful on a cold winter morning, don't they? Unfortunately, hot water melts away your skin's natural protective oils, leaving keratosis pilaris rougher and redder within hours. Keep your showers or baths to 10 to 15 minutes using warm—not hot—water. Swap out harsh deodorant bar soaps and heavily perfumed bubble baths for gentle, soap-free liquid cleansers. Running a cool-mist humidifier in your bedroom during the winter when the furnace is blasting also helps keep your skin barrier happy overnight.
✔️ What You Should Do & ❌ What to Avoid
- DO: Apply a ceramide, urea, or lactic acid lotion within 3 minutes of bathing while your skin is still damp to trap moisture inside.
- DO: Keep showers short (under 15 minutes) using lukewarm water and a fragrance-free, soap-free gentle cleanser.
- DO: Wear loose, breathable cotton clothing when exercising to prevent sweat and tight fabric friction from irritating hair follicles on your thighs and back.
- DO: Give any new keratosis pilaris treatment at least 4 to 8 weeks of consistent daily use to see smooth results, as skin cell turnover takes time.
- DON'T: Scrub your arms or legs with stiff loofahs, walnut shell scrubs, pumice stones, or aggressive dry brushes.
- DON'T: Pick, squeeze, or scratch at the bumps like pimples—there is no liquid pus inside, and squeezing causes scarring, infection, and dark spots.
- DON'T: Apply harsh adult acid peels to a baby's or young child's delicate facial cheeks without checking with your family doctor first.
🚨 When to Seek Immediate Emergency Care (Red-Flag Symptoms)
Keratosis pilaris itself is never a medical emergency. However, aggressive scratching or picking can occasionally let dangerous bacteria through broken skin, or a serious infectious rash can be mistaken for harmless bumps. If you or someone near you develops any of these red-flag symptoms, do not wait — call 911 (US & Canada), 999 or 111 (UK), or 000 (Australia) immediately, or go straight to your local Urgent Care center or the nearest hospital Emergency Room (ER / A&E):
- Signs of Spreading Skin Infection (Cellulitis): Rapidly expanding redness, intense warmth, throbbing pain, or firm swelling spreading around a scratched bump on your arm, leg, or face.
- Pus, Boils, or Golden Crusts: Bumps that suddenly swell into painful, fluid-filled boils, ooze thick yellow-green pus, or develop honey-colored crusts (impetigo).
- Systemic Infection Warnings: A high fever over 38.5°C (101.3°F), shaking chills, dizziness, confusion, or red streaks spreading up your skin from an irritated area.
- Non-Blanching Purple Rash: Tiny dark-red or purple pinpoint spots that do not fade when you press the side of a clear drinking glass firmly against the skin (a critical warning sign of a medical emergency).
- Severe Allergic Reaction (Anaphylaxis): Sudden swelling of your lips, tongue, or face, widespread hives, wheezing, or trouble breathing after applying a new skincare product.
💡 Key Take-Home Message
- The real causes of keratosis pilaris come down to a harmless, inherited quirk where natural keratin protein plugs tiny hair follicles—never poor hygiene.
- Trading hot showers and harsh body scrubs for lukewarm water and the 3-minute "soak-and-seal" moisturizing habit protects your skin barrier immediately.
- Over-the-counter chemical keratolytics like 10% urea, lactic acid, or 2% salicylic acid gently dissolve stubborn plugs over 4 to 8 weeks without scratching your skin.
- If home care leaves your skin itchy, red, or self-conscious, your Primary Care Physician (PCP) or family GP clinic can easily confirm the diagnosis and discuss prescription creams or dermatologist options.




No comments yet. Be the first to share your question or experience below.