

You wake up with a persistent, uncomfortable pressure in your lower abdomen. Within hours, a trip to the bathroom brings a sharp, scalding sensation, yet only a few painful drops pass. For millions of women and men worldwide, this sudden distress is an all-too-familiar encounter with an acute urinary tract infection (UTI).
Consider the experience of 26-year-old newlywed Sarah. Following her honeymoon, she developed severe dysuria (burning urination), constant pelvic discomfort, and cloudy, foul-smelling urine. Confused and anxious, she wondered if she had contracted a sexually transmitted infection. In consultation, her doctor reassured her: her symptoms were not an STI, but rather a classic presentation of post-coital cystitis—historically referred to as "honeymoon cystitis." Understanding what causes these infections, how to eradicate them safely, and when to seek urgent emergency care is essential for protecting your urinary system and kidney function.
⚡ Key Clinical Takeaways.
- Primary Culprit: Over 80% of uncomplicated UTIs stem from Escherichia coli (E. coli) originating in the digestive tract.
- First-Line Therapy: Confirmed bacterial cystitis requires targeted, prescription antibiotics (such as Nitrofurantoin or Trimethoprim-Sulfamethoxazole); natural remedies cannot cure active systemic infections.
- Anatomy Factor: Women have a greatly shorter urethra (approx. 4 cm vs. 20 cm in men) situated close to the anus, facilitating ascending bacterial colonization.
- Red-Flag Escalation: High fever, shaking chills, flank (side/kidney) pain, and persistent vomiting signal ascending infection (pyelonephritis) or urosepsis requiring immediate emergency intervention.
Renal function (eGFR)
Measure kidney function based on creatinine value
What Is a Urinary Tract Infection (UTI)?
A urinary tract infection is a microbial invasion affecting any structure of the urinary system: the kidneys, ureters, bladder, or urethra. Clinicians classify these infections into two primary anatomical categories:
- Lower Urinary Tract Infection (Cystitis / Urethritis): An infection confined to the bladder or urethra. This causes localized symptoms such as burning, urinary frequency, and suprapubic cramping.
- Upper Urinary Tract Infection (Pyelonephritis): An ascending infection that travels past the ureters into the renal parenchyma (the kidneys). This is a serious medical complication capable of causing permanent renal scarring or life-threatening urosepsis.
how it happens: Why Do UTIs Occur?
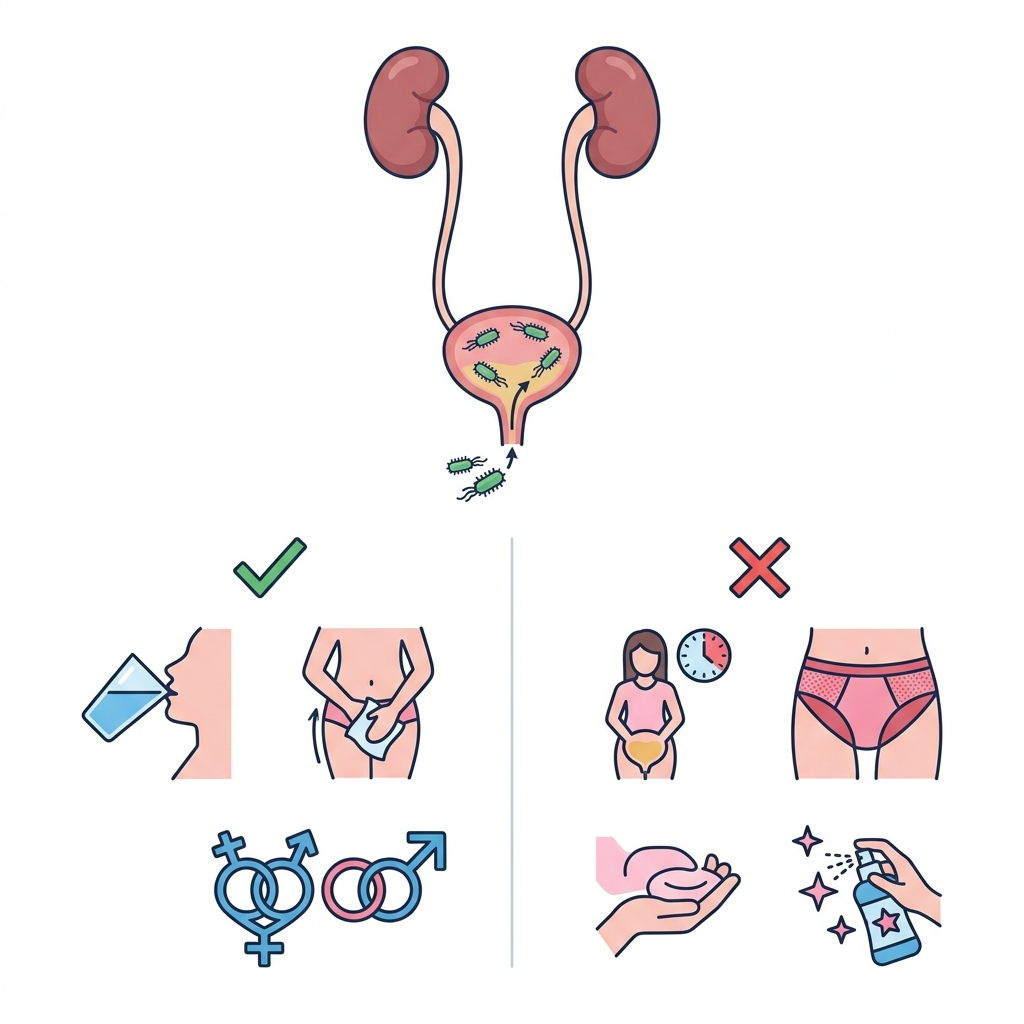
Under healthy conditions, urine is sterile, and the constant directional flow of urination flushes transient bacteria out of the urinary tract. However, specific anatomical and behavioral factors can disrupt these natural defenses.
The Role of Bacterial Migration & E. coli.
The vast majority of UTIs are ascending infections caused by uropathogenic Escherichia coli (UPEC). These bacteria naturally colonize the bowel and perianal region. Because the female urethra measures only about 4 cm (1.5 inches) and terminates near the perianal area, bacteria can easily migrate into the urethra and bladder lining (urothelium).
What Is "Honeymoon Cystitis"?
Physical friction during sexual intercourse can mechanically push bacteria from the perineum into the external urethral orifice. When intercourse frequency increases—such as during a honeymoon or a new relationship—this bacterial inoculation occurs rapidly, giving rise to acute post-coital cystitis. It is critical to recognize that a UTI is not a sexually transmitted infection (STI); it is an opportunistic infection driven by native bowel bacteria entering the urinary tract.
Recognizing the Symptoms: Lower vs. Upper Urinary Tract.
Symptom presentation varies depending on the level of anatomical involvement:
Classic Symptoms of Bladder Infection (Cystitis).
- Dysuria: A sharp, scalding burning sensation during or right away after urination.
- Urinary Urgency & Frequency: An intense, sudden urge to void, often producing only a few milliliters of urine.
- Suprapubic Discomfort: A dull, aching pain or heavy pressure in the lower pelvis and abdomen.
- Gross Appearance: Urine that appears turbid (cloudy), emits a pungent odor, or displays pink/brown tinges of micro-hematuria (blood in the urine).
🚨 Red Flags: When to Seek Immediate Emergency Care.
If bacteria ascend from the bladder to the kidneys, a lower UTI can rapidly progress into acute pyelonephritis or life-threatening urosepsis. Proceed directly to the nearest Emergency Department (A&E / ER) or call 911 (US/Canada) or 999 (UK) if you observe:
- High, Spiking Fever (>38°C / 100.4°F) with Rigors: Shivering, uncontrollable tremors, or cold sweats.
- Flank or Renal Angle Pain: Severe, unilateral or bilateral ache situated in the mid-back just below the rib cage.
- Intractable Nausea & Emesis: Inability to keep oral fluids or prescription medicines down.
- Frank Hematuria: Passing visible blood clots or heavily blood-stained urine.
- Acute Confusion, Delirium, or Lethargy: Crucial red flags in elderly adults, who may present with acute mental status shifts without classic urinary burning or fever.
Clinical Diagnosis: Lab Tests and Evaluation.
To confirm an active infection and differentiate it from conditions like interstitial cystitis, vaginitis, or urethritis caused by chlamydia or gonorrhea, clinicians rely on diagnostic laboratory testing:
- Urinalysis (Dipstick & Microscopy): Screens for leukocyte esterase (white blood cells indicating inflammation), urinary nitrites (byproducts of gram-negative bacteria such as E. coli), and red blood cells.
- Midstream Urine Culture and Sensitivity (Urine C&S): Considered the gold standard. A colony count typically exceeding 100,000 CFU/mL (colony-forming units per milliliter)—or >1,000 CFU/mL in symptomatic people—confirms a UTI and identifies the exact bacterial species along with the specific antibiotics capable of eradicating it.
Evidence-Based Medical Treatment.
While staying hydrated helps flush the bladder, an established bacterial UTI requires appropriate antimicrobial therapy prescribed by a licensed clinician. Unmanaged infections carry substantial risks of renal progression.
Prescription Antibiotics.
- First-Line Agents: Standard clinical guidelines from the Infectious Diseases Society of America (IDSA) and the NHS recommend agents such as Nitrofurantoin, Trimethoprim-Sulfamethoxazole (TMP-SMX), or Pivmecillinam for uncomplicated lower UTIs.
- Second-Line Options: Cephalosporins (e.g., Cephalexin) or Amoxicillin-Clavulanate are chosen if allergies or bacterial resistance patterns are present. Fluoroquinolones (such as Ciprofloxacin) are generally reserved for complicated infections or upper tract involvement due to safety alerts regarding tendon and nervous system adverse effects.
- Complete the Full Course: Even if dysuria resolves within 48 hours, finish all prescribed doses to prevent the emergence of antimicrobial-resistant pathogens.
Symptomatic Relief.
Over-the-counter urinary analgesics containing phenazopyridine can temporarily numb the bladder lining and relieve severe burning while antibiotics take effect. Note: Phenazopyridine harmlessly discolors urine to a bright orange-red and should not replace antibiotic therapy.
Evidence-Based Do's and Don'ts for Prevention.
Implementing targeted hygiene, fluid, and behavioral habits greatly reduces the rate of initial and recurrent bladder infections.
| Clinically Recommended (Do's). | Practices to Avoid (Don'ts). |
|---|---|
| Maintain robust hydration: eat 2 to 3 liters (68–100 fl oz) of water daily to maintain steady urine flow and mechanical clearance. | Do not hold urine: Suppressing the urge to void allows bacteria to multiply unchecked in warm, stagnant bladder urine. |
| Wipe front to back: Always cleanse from the urethra toward the perianal area after using the toilet to avoid rectal contamination. | Avoid douching and scented washes: Perfumed soaps, bubble baths, and internal douches alter protective vaginal lactobacilli and damage mucosal barriers. |
| Urinate promptly after intercourse: Voiding within 15 minutes clears bacteria that may have entered the urethral opening during sexual activity. | Avoid tight synthetic fabrics: Non-breathable nylon underwear traps sweat and moisture, creating an ideal environment for bacterial colonization. |
| Wear breathable cotton underwear: Loose-fitting natural cotton helps keep the perineal region dry and well-ventilated. | Do not stop antibiotics early: Discontinuing treatment as soon as symptoms subside can leave hardy bacteria behind, sparking recurrent infection. |





No comments yet. Be the first to share your question or experience below.